Polycystic Ovary Syndrome (PCOS): Symptoms, Causes, Diagnosis, and Treatment

Updated: 3 days ago
Medically reviewed by Dr. Baraa Alnahhal, MD · Last reviewed: October 2026
Polycystic ovary syndrome (PCOS), now also called polyendocrine metabolic ovarian syndrome (PMOS), is a hormone condition in women of childbearing age that causes irregular periods, excess androgen effects such as facial hair growth and acne, and many small fluid-filled sacs in the ovaries. A diagnosis requires at least two of these three signs. There is no cure, but weight management, hormone medicines, and fertility treatments can manage symptoms and lower the risk of diabetes and heart disease.
Quick Answer: What Is Polycystic Ovary Syndrome?
Polycystic ovary syndrome (PCOS) is a hormone condition that affects women of childbearing age, causing infrequent or long periods, excess androgen-related hair growth and many small fluid-filled sacs in the ovaries. It is diagnosed when at least two of the three main signs are present. There is no cure, but lifestyle changes and medicine manage symptoms and reduce long-term risks. [1]
What the research says
The 2023 international guideline updated how PCOS is diagnosed and managed. The guideline includes 254 recommendations and practice points, built on 77 evidence-based and 54 consensus recommendations plus 123 practice points. Key updates include allowing anti-Müllerian hormone (AMH) levels as an alternative to ultrasound in adults only, and stronger recognition of metabolic risk, cardiovascular disease, sleep apnea, and psychological features. The evidence base is still generally of low to moderate quality (Teede et al., Hum Reprod, 2023).
Lifestyle changes give modest but real improvements. A Cochrane review of 15 trials with 498 participants found that lifestyle intervention may reduce weight by about 1.68 kg (95% CI 0.70 to 2.66 kg lower; 9 trials, 353 participants) and improve the free androgen index (mean difference −1.11). The evidence was low quality, and no trial measured live birth or menstrual regularity (Lim et al., Cochrane Database Syst Rev, 2019).
Letrozole outperformed clomiphene for inducing ovulation. A meta-analysis of 29 randomized trials (3,952 women) found letrozole gave higher ovulation rates (RR 1.14), clinical pregnancy rates (RR 1.48; 95% CI 1.34 to 1.63), and live-birth rates (RR 1.49; 95% CI 1.27 to 1.74) than clomiphene, although the quality of evidence was mixed (Liu et al., Obstet Gynecol, 2023).
Research summaries are based on article abstracts retrieved from PubMed.
What Is Polycystic Ovary Syndrome?
Polycystic ovary syndrome is a hormone health issue that starts to show signs in women of childbearing age. It used to be called PCOS alone, but recent guidelines also name it polyendocrine metabolic ovarian syndrome (PMOS). [1]
If you have the condition, you may not have periods very often, or your periods may last many days. You also may have male-pattern hair growth, called hirsutism, which happens when your body has too much of a group of hormones called androgens. The condition is driven by the effects of androgen and changes in how your body uses insulin, the hormone that controls blood sugar. [1]
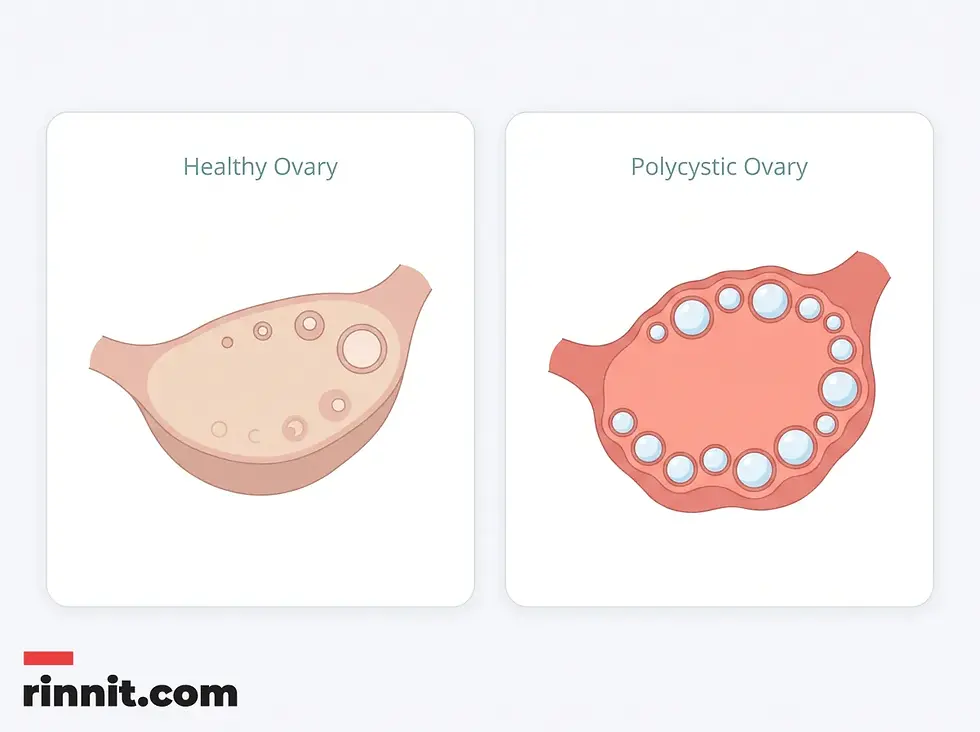
With the condition, many small sacs of fluid grow along the outer edge of the ovary. These sacs are called cysts or follicles, and they hold immature eggs. The follicles are unable to regularly release eggs. [1]
The exact cause is not known, but genetic and lifestyle factors may play a part. Early diagnosis and treatment along with weight management may lower the risk of long-term health issues, such as type 2 diabetes and heart disease. [1]
Key Fact | Detail |
What it is | A hormone condition affecting women of childbearing age |
Former name | PCOS; also now called polyendocrine metabolic ovarian syndrome (PMOS) |
Main drivers | Androgen hormone effects and insulin changes |
Ovarian feature | Many small fluid-filled sacs (follicles) holding immature eggs |
Cure status | No cure; symptoms are manageable |
Long-term risk reduction | Early diagnosis, treatment, and weight management |
What Are the Symptoms?
Symptoms often start around the time of the first menstrual period, though sometimes they develop later after periods have begun. The symptoms vary and can change over time. Some women have very severe symptoms, while others have mild symptoms or none at all. [1]
A diagnosis is made when you have at least two of the following three symptom groups.
Symptom Group | What Happens |
Irregular periods | Periods are less predictable; skipped or more than 35 days apart; fewer than eight per year; or heavy, long, frequent, or stopped periods; trouble getting pregnant |
Too much androgen effect | Extra hair on the face and body (hirsutism) in places men typically grow hair, such as the chin, sideburn area, chest, upper thighs, or back; sometimes male-pattern hair loss or severe acne |
Polycystic ovaries | Ovaries slightly bigger than usual with many small fluid-filled sacs around the edge holding immature eggs that often do not get released |
It is important to note that large ovarian cysts are not a sign of the condition. Symptoms are usually more serious in people with obesity. [1]
When should you see a doctor about PCOS?
See your healthcare professional if you are worried about your periods, if you are having trouble getting pregnant, or if you have symptoms of too much androgen. Androgen symptoms include new hair growth on your face and body, acne, and male-pattern hair loss. [1]
Sign | Why It Matters |
Irregular or missed periods | A core diagnostic symptom |
Periods lasting many days | Signals a possible hormone imbalance |
New facial or body hair growth | Androgen excess indicator |
Unexplained acne or male-pattern hair loss | Androgen excess indicator |
Difficulty getting pregnant | Fertility complication to evaluate early |
What Causes Polycystic Ovary Syndrome?
The exact cause is not known. Most experts think many things might play a role. [1]
Insulin resistance. Your body may not respond well to insulin, the hormone made in the pancreas that allows cells to use sugar, your body's main source of energy. If cells do not respond to insulin the way they typically would, blood sugar levels go up. Your body then makes more insulin to try to bring blood sugar down. One symptom of insulin resistance is dark, velvety patches of skin on the lower part of the neck, armpits, groin, or under the breasts. Feeling hungrier than usual and weight gain may be other symptoms.
Genes. Some research shows that certain genes might be linked to the condition. Having a family history may mean you are more likely to have it.
Too much androgen activity. Your body may make too much of the androgen hormones, which are at higher levels in men. Or your androgen levels may be normal, but the hormones are more active. This can cause male-pattern hair growth and some kinds of acne. As a result, ovulation may not always happen, so eggs do not develop regularly and are not released from the follicles where they develop.
Possible Cause | How It Contributes |
Insulin resistance | Cells stop responding well to insulin, raising blood sugar and insulin levels |
Genes | Certain genes may be linked; family history raises likelihood |
Too much androgen activity | Excess or overactive androgens disrupt ovulation and cause hair growth and acne |
Exact cause | Not known; most experts believe several factors play a role |
Who Is Most at Risk?
Certain factors may increase your risk of the condition. [1]
Risk Factor | How It Increases Risk |
Family history | Having family members with the condition raises your likelihood |
Overweight or obesity | Carrying extra weight puts you at risk |
Insulin resistance | May contribute to developing the condition |
Too much androgen activity | May contribute to developing the condition |
What complications can polycystic ovary syndrome (PCOS) cause?
Complications can be significant, and obesity, which is common in people with the condition, can make them worse. [1]
Complication | What Happens |
Infertility | Harder to get pregnant, though pregnancy is still possible; use birth control if not wishing pregnancy |
Pregnancy complications | Higher chance of gestational diabetes, high blood pressure during pregnancy, miscarriage, or early birth |
Liver disease (metabolic dysfunction-associated steatotic liver disease) | Fat builds up in the liver, a risk factor for cardiovascular disease |
Metabolic syndrome | High blood pressure, high fasting blood sugar, and unhealthy cholesterol or triglycerides that significantly raise heart disease and blood vessel risk |
Type 2 diabetes or prediabetes | Greater chance of high blood sugar |
Sleep apnea | Stopping breathing for short periods while sleeping |
Mental health issues | Depression, anxiety, and eating disorders can occur |
Uterine and ovarian cancer | Thickened uterus lining raises endometrial cancer risk; ovarian cancer risk is also higher |
How Can the Risk of Complications Be Lowered?
Early diagnosis and treatment along with weight management may lower the risk of long-term health issues, such as type 2 diabetes and heart disease. [1]
Stay active. Aerobic exercise and strength training help lower blood sugar levels, improve how insulin works, and may treat or even prevent insulin resistance.
Manage your weight. Weight management supports both symptom control and lower complication risk, as symptoms are usually more serious in people with obesity.
Monitor your health. Regular checks of blood pressure, glucose, cholesterol, and triglycerides, plus screening for depression, anxiety, and obstructive sleep apnea, catch complications early.
Risk-Lowering Step | What It Involves |
Early diagnosis and treatment | See a healthcare professional promptly for irregular periods or androgen symptoms |
Weight management | Maintaining a healthy weight with diet and exercise |
Regular monitoring | Blood pressure, glucose, cholesterol, and triglyceride checks; sleep apnea and mental health screening |
Physical activity | Aerobic exercise and strength training to improve insulin function |
How Is It Diagnosed?
There is no single test. Your healthcare professional is likely to start by talking about your symptoms, medicines, and other health issues. They also may ask about your menstrual periods and any weight changes. A physical exam checks for signs of male-pattern hair growth, insulin resistance, and acne. [2]
Your healthcare professional might then recommend the following.
Diagnostic Test | What It Checks |
Pelvic exam | Reproductive organs checked for masses, growths, or other changes |
Blood tests | Hormone levels measured; other causes ruled out; fasting cholesterol and triglycerides; glucose test for how your body responds to sugar |
Ultrasound | Ovaries and uterine lining thickness examined using sound waves from a wandlike device |
During a transvaginal ultrasound, you lie on your back while a wand-shaped device called a transducer is placed in your vagina to create images of your ovaries and other pelvic organs. A polycystic ovary has many small fluid-filled sacs, called follicles.
If you are diagnosed, your healthcare professional might recommend more tests for complications, including regular checks of blood pressure, glucose tolerance, and cholesterol and triglyceride levels, plus screening for depression, anxiety, and obstructive sleep apnea.
How Is It Treated?
Polycystic ovary syndrome (PCOS) has no cure, but treatment can manage symptoms and lower long-term health risks. Treatment focuses on managing symptoms and reducing the risk of long-term health issues, such as heart disease and diabetes. Your plan depends on your symptoms, current health issues, and pregnancy goals. A combination of lifestyle changes and medicine is usually recommended. [2]
Lifestyle Changes
Stay at a healthy weight. Weight loss is recommended for women with overweight or obesity. Your healthcare professional may suggest a low-calorie diet and regular exercise. Even losing a small amount of weight, such as 5% of your body weight, can improve symptoms and reduce the risk of other health issues. Exercise lowers blood sugar levels by improving how insulin works, and it can lower androgen levels and help you ovulate so that your periods are more regular. Losing weight may help your medicines work better and can help with infertility. Ask about a weight-control program and meet with a registered dietitian if recommended.
Limit calories. When losing weight, eating fewer calories is the most important thing, no matter what kind of diet you follow. Research has not shown that one diet works better than another for weight loss, as long as you are eating fewer calories overall.
Be active. Aerobic exercise and strength training help lower blood sugar levels and may treat or even prevent insulin resistance. Being active also may help you manage your weight and avoid diabetes.
Lifestyle Change | Key Benefit |
Healthy weight (even 5% loss) | Improves symptoms, lowers androgens, helps ovulation, helps medicines work better |
Limit calories | The most important part of weight loss regardless of diet type |
Aerobic and strength training | Lowers blood sugar, treats or prevents insulin resistance, manages weight |
Medicines to Regulate Periods
Combination birth control pills. Pills with both estrogen and progestin can help reduce androgen and make your menstrual cycle more regular. These medicines also can help lower your risk of endometrial cancer and improve irregular bleeding, unwanted hair growth, and acne.
Progestin therapy. Taking a progestin for 10 to 14 days every 1 to 2 months can regulate your periods and protect against endometrial cancer. Progestin therapies do not improve androgen levels and will not prevent pregnancy. Progestin-only birth control pills or a progestin-containing intrauterine device are better choices if you also wish to avoid pregnancy.
Medicine | Effect on Periods | Effect on Androgens | Prevents Pregnancy |
Combination birth control pills | Regularizes cycle | Reduces androgen | Yes |
Progestin therapy (10–14 days every 1–2 months) | Regulates periods | No | No |
Medicines to Treat Infertility
Not everyone has difficulty getting pregnant. If you are trying and have irregular periods or have not become pregnant within 6 to 12 months, your healthcare professional may suggest medicines to help you ovulate.
Medicine | How It Works |
Metformin (Glumetza, Fortamet) | Type 2 diabetes medicine that improves insulin's ability to lower blood sugar; may delay or prevent type 2 diabetes in prediabetes and help with weight loss |
GLP-1 medicines (e.g., Ozempic or Zepbound) | Help lower blood sugar and promote weight loss; usually given as a shot; stopped before pregnancy |
Letrozole (Femara) | Helps the body make more of the hormone needed to trigger ovulation |
Clomiphene | Pill taken at the beginning of your menstrual cycle; metformin may be added if it does not work |
Gonadotropins | Hormone medicines given as shots |
If needed, talk with your healthcare professional about procedures that may help you become pregnant. In vitro fertilization may be an option.
Medicines to Treat Male-Pattern Hair Growth or Acne
Birth control pills lower the amount of androgens made or reduce the activity of those hormones, which can help clear acne and reduce male-pattern hair growth.
Spironolactone (Aldactone) blocks the effects of androgens on the skin, which can help reduce male-pattern hair growth and acne. Spironolactone can cause birth defects, so effective birth control is needed while taking it. It is not recommended if you are pregnant or planning to become pregnant.
Eflornithine (Vaniqa) is a cream that can slow facial hair growth.
Hair removal options include electrolysis and laser hair removal. Electrolysis places a tiny needle in each hair follicle, and the needle sends out a pulse of electricity that destroys the follicle. Laser hair removal uses light energy to remove unwanted hair. You might need many treatments. Shaving, plucking, or using creams that dissolve unwanted hair also may help, but the results are temporary. Often hair removal and medicines are used together.
Acne treatments, including pills and creams or gels, may help improve acne. Talk to your healthcare professional about options.
Option | What It Does | Important Notes |
Birth control pills | Lower androgen production or activity | Clears acne, reduces hair growth |
Spironolactone (Aldactone) | Blocks androgen effects on skin | Can cause birth defects; effective birth control required; not for pregnancy |
Eflornithine (Vaniqa) | Cream slows facial hair growth | Used on the face |
Electrolysis | Destroys follicles with electricity pulses | May need many treatments |
Laser hair removal | Removes hair with light energy | May need many treatments |
Temporary methods | Shaving, plucking, dissolving creams | Results are temporary |
Acne medicines | Pills, creams, or gels | Discuss options with your healthcare professional |
How can people cope with PCOS and find support?
Although there is no cure, lifestyle changes and treatments can improve symptoms and reduce long-term health effects. To cope, try these strategies. [2]
Connect with others. Finding support from other people with the condition can be helpful. Whether it is an online community, a support group, or a trusted friend or family member, sharing experiences can make you feel understood and less alone.
Learn as much as you can. Learning about the condition and how it affects your body can help you feel more empowered. Turn to reliable sources such as your healthcare team to better understand your diagnosis, symptoms, and treatment.
Prioritize your mental health. Living with a chronic condition can be stressful and sometimes lead to feelings such as anxiety or depression. Talk openly with your care team about how you are feeling and do not be afraid to ask for help.
Living with the condition is challenging and different for everyone. Not all people have the same symptoms or face the same health issues. Although it does increase your risk of complications such as infertility or diabetes, it does not always mean these will happen.
Coping Strategy | How It Helps |
Connect with others | Support groups and communities reduce isolation |
Learn about the condition | Reliable information empowers your decisions |
Prioritize mental health | Open talk with your care team addresses anxiety and depression |
How should you prepare for a PCOS appointment?
You may see a specialist in female reproductive medicine, called a gynecologist. You also may see a specialist in hormone disorders, called an endocrinologist, or an infertility specialist, called a reproductive endocrinologist. [2]
What You Can Do
Before your appointment, make a list of the following items.
Preparation Item | Details |
Symptoms | What you have been having and for how long |
Period information | How often periods happen, how long they last, and how heavy they are |
All medicines and supplements | Medicines, vitamins, herbs, and other supplements, including the amount and how often |
Key personal and health information | Other health conditions, recent life changes, and stressors |
Questions to ask | Your list of questions for your healthcare professional |
Some basic questions to ask include:
What tests do you recommend?
How does the condition affect my chance of getting pregnant?
Are there any medicines that might help improve my symptoms or make it easier to get pregnant?
Are there things I can do to improve my symptoms?
How will the condition affect my health later in life?
I have other health issues. How can I manage them alongside this condition?
What to Expect From Your Doctor
Your healthcare professional is likely to ask you a number of questions, including:
Question Your Doctor May Ask | What It Helps Reveal |
What are your symptoms? How often do they happen? | Symptom pattern and frequency |
How bad are your symptoms? | Severity of the condition |
When did each symptom start? | Onset timeline |
When was your last period? | Menstrual pattern |
Have you gained weight since you first started having periods? How much, and when? | Weight history tied to hormone changes |
Does anything seem to improve your symptoms? Make them worse? | Helpful or harmful factors |
Are you trying to get pregnant, or do you wish to become pregnant? | Fertility goals that shape treatment |
Has any close blood relative, such as your mother or a sister, ever been diagnosed? | Family history and genetic risk |
Conclusion
Polycystic ovary syndrome (PCOS), now also known as polyendocrine metabolic ovarian syndrome (PMOS), is a common hormone condition of women's reproductive years that touches periods, fertility, appearance, and long-term metabolic health. It is driven by androgen hormones and insulin changes, and it requires at least two of its three hallmark signs for a diagnosis. There is no cure, but the condition is very manageable: weight loss of even 5% can meaningfully improve symptoms, hormone medicines can regulate periods and protect the uterus, dedicated fertility medicines can help you conceive, and hair and skin treatments address the visible effects. The complications, from diabetes to endometrial cancer, are real but largely preventable with early diagnosis and regular monitoring.
Your next step: If your periods are irregular, your hair growth has changed, or you have been unable to conceive after 6 to 12 months of trying, book an appointment with a gynecologist or endocrinologist and bring the symptom and period information in this guide.
Frequently Asked Questions
What is polycystic ovary syndrome?
PCOS is a hormone condition that starts to show signs in women of childbearing age. It causes infrequent or long periods, male-pattern hair growth from excess androgens, and many small fluid-filled sacs of immature eggs in the ovaries.
What is the new name, PMOS?
Health guidelines now also refer to the condition as polyendocrine metabolic ovarian syndrome (PMOS), reflecting its effects on androgen hormones, metabolism, and the ovaries.
How is PCOS diagnosed?
There is no single test. A diagnosis is made when you have at least two of three signs: irregular periods, too much androgen effect, and polycystic ovaries. Pelvic exams, blood tests, and ultrasound help confirm it.
Are large ovarian cysts a sign of PCOS?
No. Large ovarian cysts are not a sign of the condition. The cysts involved are actually many small fluid-filled sacs called follicles holding immature eggs.
What causes PCOS?
The exact cause is not known. Insulin resistance, genes, and too much androgen activity are thought to play a role.
Who is most at risk?
People with a family history of the condition, those who are overweight or have obesity, and people with insulin resistance or excess androgen activity.
What complications can PCOS cause?
Infertility, pregnancy complications, fatty liver disease, metabolic syndrome, type 2 diabetes or prediabetes, sleep apnea, mental health issues, and uterine and ovarian cancer.
Can weight loss really help?
Yes. Losing even 5% of your body weight can improve symptoms, reduce androgen levels, help you ovulate, and make your medicines work better.
What medicines help regulate periods?
Combination birth control pills (estrogen and progestin) and progestin therapy taken 10 to 14 days every 1 to 2 months.
What medicines help with fertility?
Metformin, GLP-1 medicines, letrozole, clomiphene, and gonadotropin shots. In vitro fertilization may also be an option.
Is there a cure for PCOS?
No. Treatment focuses on managing symptoms and reducing the risk of long-term health issues such as heart disease and diabetes through lifestyle changes and medicine.
Trusted Resources
Office on Women's Health — Polycystic Ovary Syndrome: federal overview of PCOS
American College of Obstetricians and Gynecologists — PCOS FAQs: practice guidance and patient FAQs
NICHD — Polycystic Ovary Syndrome Factsheet: National Institute of Child Health and Human Development factsheet
International PMOS/PCOS Evidence-Based Guideline: the international guideline referenced by clinicians
Related Reading
Laser Hair Removal: How It Works, Sessions and Results explains how laser hair removal works and what results to expect.
Birth Control Pill: Types, Effectiveness and Side Effects explains how birth control pills work and how to take them.
Pelvic Ultrasound: Types, Preparation, What It Shows and Results explains the imaging test often used to find or rule out this condition.
Testosterone Test: Types, Why It's Done, How to Prepare and What Results Mean explains the blood test used to check for high testosterone in women.
Anti-Müllerian Hormone (AMH) Test: Normal Levels by Age and What Results Mean explains how AMH estimates ovarian reserve and what results mean.
DHEAS Test (DHEA Sulfate): Why It's Done and What Results Mean explains the adrenal hormone blood test used to check for PCOS and adrenal disorders.
References
Mayo Clinic Staff. Polyendocrine metabolic ovarian syndrome (PMOS): symptoms and causes. Mayo Clinic. May 21, 2026. https://www.mayoclinic.org/diseases-conditions/pcos/symptoms-causes/syc-20353439
Mayo Clinic Staff. Polyendocrine metabolic ovarian syndrome (PMOS): diagnosis and treatment. Mayo Clinic. May 21, 2026. https://www.mayoclinic.org/diseases-conditions/pcos/diagnosis-treatment/drc-20353443
Teede HJ, Tay CT, Laven J, et al. Recommendations from the 2023 international evidence-based guideline for the assessment and management of polycystic ovary syndrome. Hum Reprod. 2023;38(9):1655-1679. PMID: 37580037. DOI: https://doi.org/10.1093/humrep/dead156
Lim SS, Hutchison SK, Van Ryswyk E, et al. Lifestyle changes in women with polycystic ovary syndrome. Cochrane Database Syst Rev. 2019;3(3):CD007506. PMID: 30921477. DOI: https://doi.org/10.1002/14651858.CD007506.pub4
Liu Z, Geng Y, Huang Y, et al. Letrozole compared with clomiphene citrate for polycystic ovarian syndrome: a systematic review and meta-analysis. Obstet Gynecol. 2023;141(3):523-534. PMID: 36735392. DOI: https://doi.org/10.1097/AOG.0000000000005070
Medical disclaimer
This article is for informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have about a medical condition.



Comments