Anemia of Chronic Disease: Why Inflammation Traps Your Iron, Who's at Risk, and How Treatment Works

Updated: Nov 11
Medically reviewed by Dr. Baraa Alnahhal, MD · Last reviewed: October 2026
Editorial note: This article is for general education only. It is not medical advice, a diagnosis, or a treatment plan. Anemia of chronic disease occurs in people who already live with long-term illness, and all testing and treatment decisions should be made with your healthcare provider.
Quick Answer: What Is Anemia of Chronic Disease?
Anemia of chronic disease is a form of anemia caused by long-term inflammation from an illness lasting more than three months, such as cancer or chronic kidney disease. The inflammation traps iron in storage cells, so the body can't use it to make red blood cells. It is usually mild, and most cases resolve when the underlying disease improves.
What the research says
Anemia becomes more common as kidney disease worsens. A US national survey found anemia in 15.4% of people with chronic kidney disease, twice the rate in the general population (7.6%), rising from 8.4% at stage 1 to 53.4% at stage 5. Only 22.8% of those with anemia reported recent treatment (Stauffer and Fan, PLoS One, 2014).
Pushing hemoglobin higher with injections is not always better. In the TREAT trial of 4,038 people with diabetes, kidney disease and anemia, raising hemoglobin to about 13 g/dL with darbepoetin did not reduce death, heart events or kidney failure, and nearly doubled the risk of stroke (hazard ratio 1.92), though fewer transfusions were needed (Pfeffer et al., New England Journal of Medicine, 2009).
What Exactly Is Anemia of Chronic Disease?
Red blood cells deliver oxygen to every organ, and each one lives about 120 days before being replaced [1]. Your body normally recycles the iron from old red blood cells to build new ones. In anemia of chronic disease, that recycling breaks down: inflammatory signals cause storage cells called macrophages to trap the recycled iron instead of releasing it [1]. Your iron isn't gone — it's locked away — and the result is too few red blood cells.
Providers may also call this condition anemia of inflammation or anemia of inflammation and chronic disease [1].
Term you might hear | What it means |
Anemia of chronic disease (ACD) | Anemia caused by a long-term inflammatory illness [1] |
Anemia of inflammation | Same condition — newer preferred name [1] |
Iron-deficiency anemia | Anemia from genuinely low iron stores (different condition) [1] |
Anemia of inflammation and chronic disease | Full formal name sometimes used by providers [1] |

In anemia of chronic disease, long-term inflammation from conditions like cancer, kidney disease, heart failure, and autoimmune disease causes macrophages to trap recycled iron, starving the bone marrow of the raw material needed to build red blood cells. It is the second most common anemia worldwide, affects about 1 million Americans over 65, and most cases are mild and resolve when the underlying disease improves.
How Common Is Anemia of Chronic Disease?
ACD is the second most common type of anemia in the world, behind only iron-deficiency anemia [1]. It overwhelmingly affects older adults, because long-term illness is common in that age group.
Measure | Estimate | Evidence |
Rank among all anemias | 2nd most common (after iron deficiency) [1] | Cleveland Clinic [1] |
Americans 65+ affected | ~1 million [1] | Cleveland Clinic [1] |
Share of all anemia cases | ~30.7% [2] | Clinical practice study [2] |
Risk in people 80+ | ~4x higher than general population [2] | Clinical practice study [2] |
Anemia of inflammation in community-dwelling adults | ~12% [3] | PMC review, 2024 [3] |
Anemia in hospitalized patients | ~40–52% [3] [4] [5] | Multiple hospital studies [3] [4] [5] |
Anemia in nursing home residents | ~47% [3] | PMC review, 2024 [3] |
Medicare beneficiaries with 2+ chronic conditions | 68.4% [6] | CDC PCD, 2013 [6] |
The underlying math is sobering: about 85% of older adults have at least one chronic condition, and 68% of Medicare beneficiaries carry two or more [6]. That's the pool from which anemia of chronic disease draws its patients. Among hospitalized patients, anemia of chronic disease is frequently more prevalent than iron-deficiency anemia — a reversal of the pattern seen in the general population [5].
Underlying disease | Anemia prevalence in that group | Evidence |
Chronic kidney disease (late stages) | ~33% [7] | Springer, 2023 [7] |
Heart failure (stable, outpatient) | ~30% [8] | NIH review, 2022 [8] |
Heart failure (hospitalized) | ~50% (range 9–69.6%) [8] [9] | NIH review; ACC, 2021 [8] [9] |
Nursing home residents (all-cause) | ~47% [3] | PMC review, 2024 [3] |
What Diseases Cause Anemia of Chronic Disease?
Any chronic illness that causes inflammation can cause ACD — the disease itself doesn't have to damage your blood [1]. The clinical guidance identifies these categories.
Category | Examples |
Cancer | Any cancer causing chronic inflammation [1] |
Kidney disease | Chronic kidney disease [1] |
Heart disease | Heart failure (congestive heart failure) [1] |
Autoimmune diseases | Rheumatoid arthritis, lupus, vasculitis, sarcoidosis, inflammatory bowel disease (Crohn's disease, ulcerative colitis) [1] |
Infections | Any type of ongoing infection [1] |
Other | Having obesity [1] |
Why the underlying disease causes anemia | Mechanism |
Iron trapping | Macrophages trap recycled iron instead of releasing it [1] |
Slower production | Inflammation slows bone marrow red blood cell production [1] |
Shorter lifespan | Red blood cells die sooner than their usual 120 days [1] |
What Are the Symptoms?
Symptoms mirror iron-deficiency anemia — but many people notice nothing at all, or only feel symptoms during exercise [1].
Symptom | How it shows up |
Extreme tiredness or weakness | Too weak to manage day-to-day activities [1] |
Shortness of breath | Especially with exertion [1] |
Pale skin | Lighter than your usual skin tone [1] |
Unexplained sweating | Feeling sweaty for no reason [1] |
Dizziness or faintness | Feeling lightheaded or faint [1] |
Headaches | Recurring or persistent [1] |
The practical takeaway: if you live with a chronic illness and develop unexplained fatigue, don't assume it's "just the disease." Anemia may be a treatable layer underneath [1].

Symptoms of anemia of chronic disease — fatigue, shortness of breath, pale skin, unexplained sweating, dizziness, headaches — often go unnoticed or get attributed to the underlying illness itself. Many people feel symptoms only during exercise. Because the symptoms look identical to iron-deficiency anemia, blood tests are essential to tell them apart: ACD shows low serum iron but normal or high ferritin and low iron-binding capacity, while iron deficiency shows low ferritin and high iron-binding capacity.
How Is It Different From Iron-Deficiency Anemia?
This distinction matters because the treatments are different — and taking iron for ACD usually doesn't help [1]. The lab patterns are mirror images.
Lab value | Anemia of chronic disease | Iron-deficiency anemia |
Serum iron | Low [1] | Low [1] |
Serum ferritin (iron stores) | Normal or high [1] | Low [1] |
Iron-binding capacity | Low [1] | High [1] |
Reticulocyte count (new RBCs) | Low [1] | Low [1] |
Where the iron is | Trapped in storage cells [1] | Genuinely depleted [1] |
In other words: with ACD, your body has iron — it just can't use it. With iron-deficiency anemia, the iron stores are actually empty. A bone marrow biopsy (high iron stores + low serum iron) confirms ACD when blood tests are ambiguous [1].
How Is Anemia of Chronic Disease Diagnosed?
Providers rely on a panel of blood tests — a single hemoglobin number isn't enough [1].
Test | Normal range | What it shows in ACD |
Hemoglobin | 12–17.4 g/dL [1] | Low — confirms anemia [1] |
Serum iron | 60–170 mcg/dL [1] | Low [1] |
Reticulocyte count | Varies [1] | Low — marrow under-producing [1] |
Iron-binding capacity | 250–450 mcg/dL [1] | Low — key ACD signature [1] |
Serum ferritin | 20–200/500 ng/mL [1] | Normal or high — key ACD signature [1] |
EPO level | Varies [1] | Checked if hemoglobin is low [1] |
If your hemoglobin is low, your provider may also check erythropoietin (EPO) — the hormone your kidneys make to drive red blood cell production [1]. A bone marrow biopsy may follow if blood tests can't settle the picture [1].
How Is Anemia of Chronic Disease Treated?
The central principle: treat the underlying disease, and the anemia often resolves on its own [1]. Anemia-specific therapies step in when the underlying condition can't fully reverse it.
Treatment | When it's used | Caveats |
Treat the underlying disease | First-line for everyone [1] | Often eliminates the anemia and its symptoms [1] |
Blood transfusion | Severe anemia, short-term [1] | Not a long-term solution: iron overload and infection risk [1] |
Synthetic EPO therapy | Boosts red blood cell production [1] | Common for cancer- or kidney-disease-related anemia [1] |
Iron supplements | Combined with EPO therapy [1] | Iron alone usually doesn't fix ACD [1] |
People with anemia caused by cancer or chronic kidney disease often need different or additional treatment beyond the standard approach [1].
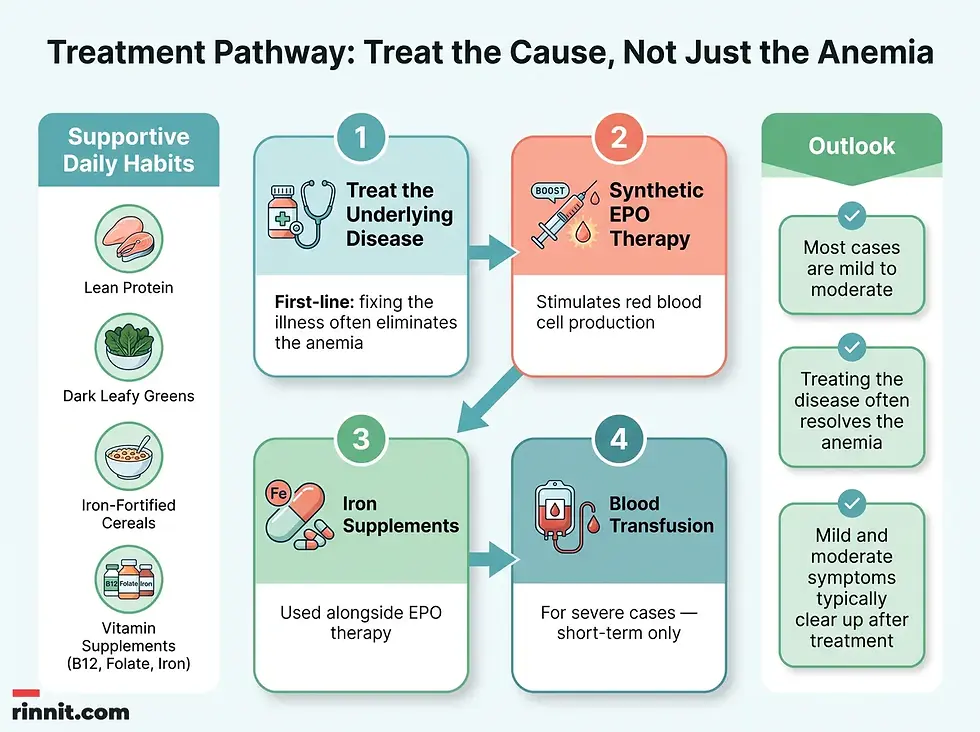
The first-line treatment for anemia of chronic disease is treating the underlying condition — which often eliminates the anemia entirely. When more is needed, providers may use synthetic EPO therapy to stimulate red blood cell production, add iron supplements alongside EPO, or use blood transfusions for severe short-term correction. EPO-type medicines carry an FDA boxed warning: pushing hemoglobin above about 11 g/dL raises the risk of stroke, heart attack, blood clots and death, so doctors use the lowest dose that avoids transfusions. Because most cases are mild to moderate, and most resolve with treatment of the underlying disease, the outlook is generally favorable.
Can It Be Prevented?
Because ACD is a consequence of the underlying illness, it generally can't be prevented directly [1]. But supporting your overall health helps your body cope [1].
Daily habit | Why it helps |
Lean protein (chicken, turkey, beans) | Building blocks for red blood cells [1] |
Dark leafy greens (spinach, kale) | Natural iron and folate [1] |
Iron-fortified bread and cereal | Steady iron intake [1] |
Vitamin supplements (B12, folate, iron) | Covers baseline needs [1] |
These don't prevent ACD — but they prevent your body's iron stores from compounding the problem [1].
When Should You Contact Your Provider?
Reach out if you live with a chronic illness and develop unusual fatigue, shortness of breath, dizziness, pale skin, unexplained sweating, or headaches [1]. Ask specifically whether a blood test might explain your symptoms — anemia is a common, treatable layer underneath chronic disease [1]. If you've been told you have anemia, ask whether iron studies (ferritin, iron-binding capacity) have been checked to determine which type you have [1].
What Is the Outlook?
The outlook is encouraging for most people. Most cases of ACD are mild or moderate, and treating the underlying condition usually resolves the anemia and its symptoms [1].
Outlook factor | Detail |
Typical severity | Most people have mild anemia [1] |
Resolution | Treating the underlying disease often eliminates the anemia [1] |
After treatment | Mild and moderate symptoms typically clear up [1] |
Severe cases | May need EPO therapy, iron supplements, or transfusion [1] |
Who to watch | Adults 65+, especially with cancer, CKD, heart failure, or autoimmune disease [1] |
Key Takeaways
Anemia of chronic disease happens when long-term inflammation — from cancer, kidney disease, heart failure, autoimmune disease, or chronic infection — traps your body's recycled iron inside storage cells, starving the bone marrow of the raw material it needs to make red blood cells. It's the second most common anemia in the world and affects an estimated 1 million Americans over age 65. Most cases are mild and symptom-free, which is why it's found on routine bloodwork rather than reported by patients. The defining lab signature — low serum iron but normal-to-high ferritin — separates it from iron-deficiency anemia and changes the treatment: fix the underlying disease, and the anemia often follows. Severe cases may need synthetic EPO, iron supplements, or a transfusion.
If you live with a chronic illness and notice unusual fatigue, shortness of breath, or pale skin, ask your provider about a blood test — and ask whether your anemia type has been confirmed with ferritin and iron-binding capacity tests.
Frequently Asked Questions
Can anemia of chronic disease be cured?
Often, yes — indirectly. Treating the underlying disease that causes the inflammation often eliminates the anemia and its symptoms entirely [1]. Because the anemia is a consequence, not a separate disease, controlling the root cause is the cure for most people.
Is it the same as iron-deficiency anemia?
No — and this distinction changes treatment. Both show low blood iron, but ACD shows normal or high ferritin (iron stores are full but trapped), while iron-deficiency anemia shows low ferritin (stores are truly empty) [1]. Taking iron tablets helps iron deficiency but usually doesn't fix ACD [1].
Can I have anemia even if my iron levels look normal?
Yes. That's the signature of ACD: your serum iron is low but your ferritin — the storage marker — is normal or even high [1]. The iron is there; inflammation has locked it away. That's why a full iron panel matters, not just one number.
Why does chronic inflammation trap iron?
Inflammation activates storage cells called macrophages, which hold onto recycled iron instead of releasing it for new red blood cell production [1]. Chronic disease can also shorten red blood cell lifespan and slow bone marrow output [1].
How common is it in hospitalized patients?
Very. Anemia affects roughly 40–52% of hospitalized patients, and anemia of chronic disease is often more prevalent than iron-deficiency anemia in that setting [3] [4] [5]. About 47% of nursing home residents have anemia [3].
Can heart failure or kidney disease alone cause it?
Yes. Anemia affects ~30% of stable heart failure patients and ~50% of hospitalized ones [8] [9], and ~33% of late-stage chronic kidney disease patients [7]. These are among the most common underlying causes of ACD [1].
Will iron supplements fix it?
Usually not on their own [1]. Iron supplements are sometimes combined with synthetic EPO therapy for cancer- or kidney-disease-related anemia [1], but the first-line treatment is always the underlying disease [1].
What blood tests confirm the diagnosis?
A panel: hemoglobin (low), serum iron (low), reticulocyte count (low), iron-binding capacity (low), and ferritin (normal or high) [1]. A bone marrow biopsy — showing high iron stores with low serum iron — confirms ACD when blood tests are unclear [1].
What are the symptoms of anemia of chronic disease?
Many people notice no symptoms, or only feel tired, weak, short of breath, or dizzy during activity. Pale skin and headaches can also occur. Get emergency care for chest pain, fainting, or severe shortness of breath.
What conditions can cause anemia of chronic disease?
Long-term conditions that cause inflammation are the usual cause, such as infections, autoimmune diseases like rheumatoid arthritis, cancer, kidney disease, and heart failure.
What else should you read about anemia of chronic disease?
Related Reading
Learn more in our guide to RDW Blood Test: What It Measures, Normal Range and High RDW Results.
Iron Blood Tests: Types, What Results Mean and How to Prepare explains the blood tests used to measure iron levels and stores.
Transferrin Saturation (TSAT) Test: Normal Range and What Results Mean explains the iron test that helps detect iron deficiency and iron overload.
Learn more in our guide to Reticulocyte Count: Normal Range, Low and High Results Explained.
Ferritin Test: Normal Ferritin Levels and What Low or High Results Mean explains the blood test that measures your stored iron, normal ferritin levels and what low or high results mean.
Peripheral Blood Smear: Why It's Done, How It Works and What It Shows explains the microscope test that examines the shape and number of red cells, white cells and platelets.
References
Cleveland Clinic. Anemia of Chronic Disease: Symptoms, Treatment & Causes. Cleveland Clinic. April 19, 2022. https://my.clevelandclinic.org/health/diseases/14477-anemia-of-chronic-disease
Sisodia R, et al. Prevalence of Anemia of Chronic Diseases (ACD) in Patients with Hemoglobin Levels Below 10 g/dL. Journal of Contemporary Clinical Practice. 2025;11(5):342-346. Not indexed in PubMed. https://jccpractice.com/article/prevalence-of-anemia-of-chronic-diseases-acd-in-patients-with-hemoglobin-levels-below-10-g-dl-689/
Wacka E, et al. Anemia and Its Connections to Inflammation in Older Adults: A Review. Journal of Clinical Medicine. 2024;13(7):2049. PMID 38610814. https://doi.org/10.3390/jcm13072049
Mohamed AA. Prevalence and Comorbidities of Anemia in Hospitalized Adults. Cureus. 2025;17(2):e79568. PMID 40151719. https://doi.org/10.7759/cureus.79568
Kandiya A, et al. Prevalence and Clinical Outcomes of Anemia of Chronic Disease Versus Iron Deficiency Anemia in Hospitalized Patients: A Cross-Sectional Analysis. European Journal of Cardiovascular Medicine. 2025;15(10):55-59. Not indexed in PubMed. https://healthcare-bulletin.co.uk/article/prevalence-and-clinical-outcomes-of-anemia-of-chronic-disease-versus-iron-deficiency-anemia-in-hospitalized-patients-a-cross-sectional-analysis-4303/
Lochner KA, et al. Prevalence of multiple chronic conditions among Medicare beneficiaries, United States, 2010. Preventing Chronic Disease. 2013;10:E61. PMID 23618541. https://doi.org/10.5888/pcd10.120137
Gerhardt LMS, et al. Prevalence and prognostic impact of chronic kidney disease and anaemia across ACC/AHA precursor and symptomatic heart failure stages. Clinical Research in Cardiology. 2023;112(7):868-879. PMID 35648270. https://doi.org/10.1007/s00392-022-02027-w
Siddiqui SW, et al. Anemia and Heart Failure: A Narrative Review. Cureus. 2022;14(7):e27167. PMID 36017290. https://doi.org/10.7759/cureus.27167
Silver MA, Anker SD. Anemia and Heart Failure: Guidance for Clinicians and Trialists. American College of Cardiology. July 6, 2021. https://www.acc.org/latest-in-cardiology/articles/2021/07/06/12/18/anemia-and-heart-failure
Zaninetti C, et al. Prevalence of anemia in hospitalized internal medicine patients: Correlations with comorbidities and length of hospital stay. European Journal of Internal Medicine. 2018;51:11-17. PMID 29153343. https://doi.org/10.1016/j.ejim.2017.11.001
Stauffer ME, et al. Prevalence of anemia in chronic kidney disease in the United States. PLoS One. 2014;9(1):e84943. PMID 24392162. https://doi.org/10.1371/journal.pone.0084943
Pfeffer MA, et al. A trial of darbepoetin alfa in type 2 diabetes and chronic kidney disease. New England Journal of Medicine. 2009;361(21):2019-2032. PMID 19880844. https://doi.org/10.1056/NEJMoa0907845
Medical disclaimer
The information provided in this article is for educational purposes only and should not be used as a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition.



Comments