Vaginal Atrophy (Genitourinary Syndrome of Menopause): Symptoms, Causes & Treatment — Complete Guide

Updated: 3 days ago
Medically reviewed by Dr. Baraa Alnahhal, MD · Last reviewed: October 17, 2026
Quick Answer
Vaginal atrophy is the older term for thinning and drying of the vagina's inner lining, usually after menopause, now recognized as part of genitourinary syndrome of menopause (GSM). It is caused by lower estrogen levels, which make tissues thinner and more fragile. It can cause dryness, burning, painful sex and urinary problems, and moisturizers or topical estrogen can bring relief.
What the research says
Genitourinary syndrome of menopause is very common, yet often under-recognized and undertreated. A systematic review of 27 studies found that the prevalence of GSM-related symptoms such as vaginal dryness, irritation, itching, and painful sex ranged from 13% to 87%. Over-the-counter lubricants and moisturizers were the most popular treatments (24.0%–85.5% of women), followed by low-dose vaginal estrogens (4.8%–35.0%); vaginal health was rarely discussed at doctor visits, and most women with symptoms were dissatisfied with the treatment they had used. (Mili et al., Menopause, 2021) [3]
Vaginal estrogen is the best-studied treatment, and it outperforms moisturizers when symptoms are more than mild. A systematic review of 44 studies found that, compared with placebo, vaginal estrogens improved dryness, painful sex, urinary urgency and frequency, and urinary incontinence, and lowered urinary tract infection rates. The different preparations had similar efficacy and safety, and women with two or more symptoms improved substantially more with vaginal estrogen than with nonhormonal moisturizers, while those with one or minor complaints improved similarly with either (Rahn et al., Obstet Gynecol, 2014) [4]. A 2024 review of 46 randomized trials found low-certainty evidence that vaginal DHEA, oral ospemifene, and vaginal moisturizers may also improve dryness, but most studies lasted 12 weeks or less and long-term data are scarce (Danan et al., Ann Intern Med, 2024) [5].
For breast cancer survivors, vaginal estrogen has not been linked to higher recurrence in pooled observational data. A meta-analysis of 8 observational studies found no increased risk of breast cancer recurrence with vaginal estrogen (6 articles, 24,060 patients; pooled unadjusted OR 0.48; 95% CI 0.23–0.98), of breast cancer mortality (OR 0.60; 95% CI 0.18–1.95), or of overall mortality (Beste et al., Am J Obstet Gynecol, 2025) [6]. A second meta-analysis of 7 articles (118,659 survivors, 6,358 treated with vaginal estrogen) likewise found no significant increase in recurrence (RR 0.87; 95% CI 0.67–1.11) (Santos et al., Rev Bras Ginecol Obstet, 2025) [7]. Both rely on observational studies, so the decision should still be made with the oncologist.
At a Glance: Vaginal Atrophy Summary
Topic | Key Facts |
What it is | Thinning and drying of the vagina's inner lining, usually after menopause; now part of genitourinary syndrome of menopause (GSM) |
Old names | Vaginal atrophy, atrophic vaginitis (terms no longer used) |
Root cause | Less estrogen — tissues become thinner, drier, less elastic, and more fragile |
When estrogen can drop | Perimenopause, after menopause, after both ovaries removed, during breastfeeding, from some medicines or cancer treatments |
Common symptoms | Dryness, burning, itching, unusual discharge, pain during sex, urinary urgency or leaking, more frequent infections |
Who's at higher risk | Smokers, people with no vaginal births, and people with no sexual activity |
Diagnosis | Pelvic exam, urine test, vaginal acid balance test |
First-line treatment | Over-the-counter vaginal moisturizers and lubricants |
Prescription options | Topical vaginal estrogen (cream, suppository, ring, tablet), ospemifene, prasterone, systemic estrogen, vaginal dilators, topical lidocaine |

What Is Vaginal Atrophy?
Vaginal atrophy used to be the medical term for thinning and drying of the vagina's inner lining, often after menopause. Another name for it was atrophic vaginitis. These terms are no longer used.
Today, the physical changes those terms described are considered part of a group of symptoms that affect the genitals and lower urinary tract, called genitourinary syndrome of menopause (GSM). GSM happens when the body has less of the hormone estrogen, and it can involve painful sex, a frequent or urgent need to urinate, and other distressing symptoms.
The most important message: having less estrogen doesn't mean you have to put up with the discomfort. Treatment can bring relief.
Vaginal Dryness: What Changes in the Tissues
Typically, the vaginal lining consists of healthy tissues that are several layers thick and naturally moist. A dry vaginal lining becomes thinner and loses natural moisture — making it less elastic and more fragile.
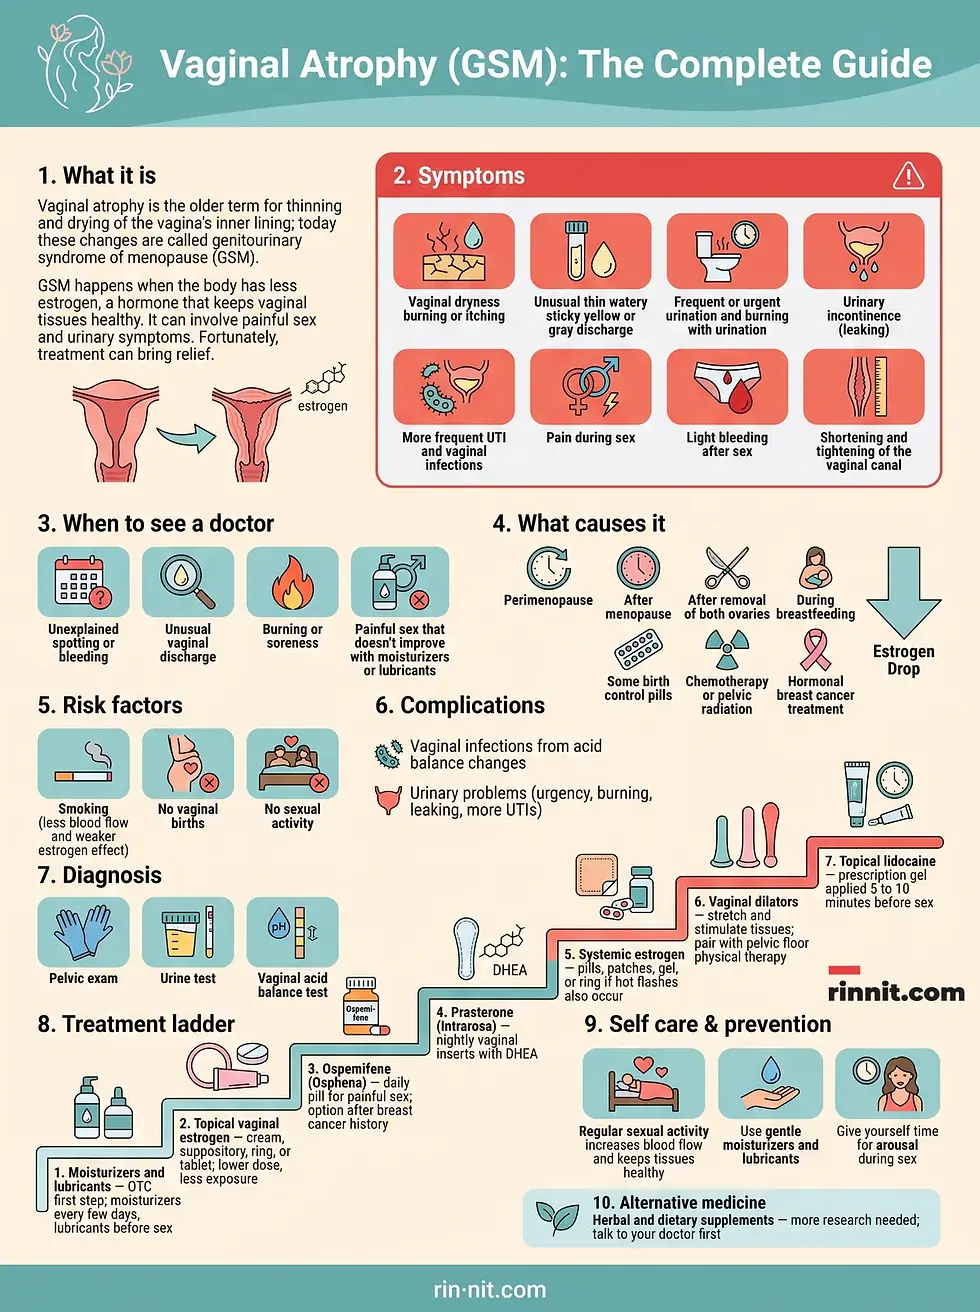
Symptoms: What GSM Can Feel Like
Genitourinary syndrome of menopause symptoms can include:
Dryness, burning or itching in the vagina
Thin, watery, sticky, yellow or gray fluid that comes out of the vagina
Frequent or urgent need to urinate, or a burning feeling during urination
Losing control of the bladder, also called urinary incontinence
More-frequent infections of the urinary tract and vagina
Pain during sex due to less lubrication, or light bleeding after sex
Shortening and tightening of the vaginal canal
These symptoms can appear at different times. They might begin to bother you during the years leading up to menopause (perimenopause), or they might not become a problem until a few years into menopause. Although the condition is common, not everyone who goes through menopause gets GSM — and regular sexual activity or masturbation can help keep vaginal tissues healthy.
When to See a Doctor
Many people have GSM after menopause, yet few seek treatment — some might feel embarrassed to talk with their healthcare professional about their symptoms. But it's important to get the help that you deserve.
Make an appointment if you have:
Light spotting or bleeding for no clear reason
Unusual fluid that comes out of the vagina
Burning or soreness
Also make an appointment if you have painful sex that doesn't get better after you use a vaginal moisturizer, a water-based lubricant, or a silicone-based lubricant.
Causes: The Estrogen Connection
Genitourinary syndrome of menopause happens when the body makes less estrogen. Lower estrogen causes the tissues in the vagina to become thinner, drier, less elastic and more fragile.
A drop in estrogen levels may happen for any of the following reasons:
Timing or Trigger | How Estrogen Drops |
After menopause | The natural end of menstrual periods |
Perimenopause | During the years leading up to menopause |
After surgery | Removal of both ovaries leads to early menopause |
During breastfeeding | Hormone levels shift while nursing |
Certain medicines | Some medicines, such as some birth control pills, can affect estrogen levels |
Cancer treatment | After chemotherapy or pelvic radiation therapy for cancer |
Breast cancer therapy | As a side effect of hormonal treatment for breast cancer |
Risk Factors
Certain factors may play a role in GSM:
Smoking. Cigarette smoking affects blood flow — less blood and oxygen may reach the vagina and other nearby areas. Smoking also reduces the effects of the estrogen your body makes.
No vaginal births. People who have never given birth through the vagina may be more likely to develop GSM symptoms than those who have had vaginal births.
No sexual activity. Sex or masturbation boosts blood flow and makes tissues in the vagina more elastic.
Complications
Genitourinary syndrome of menopause raises your risk of:
Vaginal infections — changes in the acid balance of your vagina make vaginal infections more likely.
Urinary problems — changes in the urinary tract linked with GSM can play a role. You might need to urinate more often or urgently, and it might burn when you go. Some people with GSM also leak urine or have more urinary tract infections.
Prevention
Regular sexual activity, either with or without a partner, may help prevent genitourinary syndrome of menopause. Sexual activity increases blood flow to the vagina, which helps keep tissues in the vagina healthy.
How Is Vaginal Atrophy Diagnosed?
Diagnosis of genitourinary syndrome of menopause may involve three straightforward evaluations:
Test | What Happens |
Pelvic exam | A healthcare professional feels your pelvic organs and does a visual exam of your vulva, vagina and cervix — gloved fingers inside the vagina while pressing on the stomach area lets the provider check the uterus, ovaries and other pelvic organs |
Urine test | Your urine is collected and tested if you have urinary symptoms |
Acid balance test | A sample of fluids from your vagina is taken, or a paper indicator strip is placed in your vagina, to test its acid balance |
Treatment: A Step-by-Step Ladder of Relief
To treat genitourinary syndrome of menopause, your healthcare professional might recommend that you first try a remedy you can buy without a prescription. If that doesn't help ease your symptoms, you may opt for a hormone treatment, other prescription medicine, or a device to stimulate and stretch vaginal tissues called a vaginal dilator.
Step 1: Vaginal Moisturizers and Lubricants
As a first step, you might try one of these over-the-counter products:
Vaginal moisturizers can help restore some moisture to your vagina. You may have to use the moisturizer every few days, and its effects tend to last a bit longer than those of a lubricant.
Water- or silicone-based lubricants can be used just before sex to ease pain and friction. Choose lubricants that don't contain glycerin or warming ingredients such as capsaicin — your vagina may get irritated if you're sensitive to these. And stay away from petroleum jelly or other oil-based products if you're also using condoms; these can break down latex condoms on contact.
Step 2: Topical (Vaginal) Estrogen
Topical estrogen — also called vaginal estrogen — is a lab-made version of the hormone that goes directly into the tissues of the vagina. Compared to estrogen taken by mouth, vaginal estrogen works at lower doses and limits your overall exposure to estrogen, because less of the hormone reaches the bloodstream. It also may provide better direct relief of symptoms.
Because all the forms seem to work equally well, you and your healthcare professional can decide which one is best for you:
Form | How It's Used |
Vaginal estrogen cream (Estrace, Premarin) | Inserted into the vagina with an applicator, usually at bedtime — most often daily for 1 to 3 weeks, then 1 to 3 times a week after that |
Vaginal estrogen suppositories (Imvexxy) | Placed about 2 inches into the vagina daily for two weeks, then twice a week |
Vaginal estrogen ring (Estring) | A soft, flexible ring inserted into the upper part of the vagina that releases a steady dose of estrogen; replaced about every three months (note: a different, higher-dose ring called Femring is a system-wide treatment rather than a topical one) |
Vaginal estrogen tablet (Vagifem, Yuvafem) | Placed in the vagina with an applicator — for instance, daily for the first two weeks, then twice a week after that |
Step 3: Ospemifene (Osphena)
Taken daily as a pill, ospemifene can help relieve painful sex symptoms in those with moderate to severe GSM. It carries a boxed warning about endometrial cancer, stroke and blood clots, and it is not an option for women who have had a history of estrogen-dependent breast cancer.
Step 4: Prasterone (Intrarosa)
These vaginal inserts deliver the hormone DHEA directly to the vagina to help ease painful sex. DHEA is a hormone that helps the body make other hormones, including estrogen. Prasterone is used nightly for moderate to severe vaginal atrophy.
Step 5: Systemic Estrogen Therapy
Sometimes, vaginal dryness is linked with other symptoms of menopause, such as moderate or severe hot flashes. If you have all of these symptoms, your healthcare professional may recommend estrogen pills, patches or gel, or a higher-dose estrogen ring. Estrogen taken by mouth, or as a patch or gel onto the skin, enters your entire system. Ask your healthcare professional to talk with you about the risks and benefits. If you still have your uterus, you will need another hormone called progestin along with estrogen.
Step 6: Vaginal Dilators
These devices stimulate and stretch the vaginal tissues and underlying muscles to reverse narrowing of the vagina. You can use them along with estrogen therapy. If painful sex is a concern, vaginal dilators may relieve discomfort by stretching the vagina. You can buy them without a prescription — but if your symptoms are very painful, pelvic floor physical therapy also may help. Your provider or a pelvic physical therapist can teach you how to use dilators.
Step 7: Topical Lidocaine
This prescription ointment or gel can ease pain from sex. You put it on the opening of the vagina 5 to 10 minutes before sex.
Treatment Step | What It Is | Key Details |
Moisturizers & lubricants | Over-the-counter first step | Moisturizers every few days; lubricants before sex — avoid glycerin, warming ingredients, and oil-based products with condoms |
Topical vaginal estrogen | Cream, suppository, ring, or tablet | Lower doses than oral estrogen; all forms work equally well |
Ospemifene (Osphena) | Daily pill | For moderate to severe GSM; not for women with a history of breast cancer |
Prasterone (Intrarosa) | Nightly vaginal inserts with DHEA | For moderate to severe vaginal atrophy |
Systemic estrogen | Pills, patches, gel, or higher-dose ring | When hot flashes also occur; discuss risks and benefits; progestin needed if you have a uterus |
Vaginal dilators | Stretching devices (OTC) | Reverse narrowing; combine with pelvic floor physical therapy for very painful symptoms |
Topical lidocaine | Prescription gel or ointment | Applied to the opening of the vagina 5 to 10 minutes before sex |
If You've Had Breast Cancer
If you have a history of breast cancer, tell your healthcare professional and think about these options:
Nonhormonal treatments — try moisturizers and lubricants as a first choice.
Vaginal dilators — these devices stimulate and stretch the tissues and muscles of the vagina and don't add hormones to the body.
Vaginal estrogen — your cancer specialist (oncologist) can talk with your primary healthcare professional about whether low-dose vaginal estrogen might help. It may be an option if hormone-free treatments don't ease your symptoms. For most women, there's minimal risk with low-dose estrogen of breast cancer coming back.
Systemic estrogen therapy — generally isn't recommended, especially if your breast cancer was sensitive to hormones.
Self Care
If your vagina feels dry or irritated, you may get relief if you:
Try a moisturizer. This can restore some moisture to your vagina.
Use a water- or silicone-based lubricant to reduce pain during sex.
Give yourself time to become aroused during sex. The natural lubrication that happens when you get aroused can help reduce symptoms of dryness or burning.
Alternative Medicine
Some alternative medicines are used to treat vaginal dryness and irritation linked with menopause. But more research is needed to find out if they work well.
Talk with your doctor or other healthcare professional before you take any herbal or dietary supplements. Some may affect other medicines you take, putting your health at risk.
Preparing for Your Appointment
You'll probably start by talking about your symptoms with your primary doctor or other healthcare professional. If you aren't already seeing a specialist in women's health, such as a gynecologist, you may be referred to one.
What You Can Do
Make a list of your symptoms, including those that may not seem related to the reason for your appointment.
Make a note of key personal information, including any major stresses or recent life changes.
Make a list of all medicines that you take — prescription and nonprescription drugs, vitamins, and supplements — and note the dose of each.
Think about taking a family member or friend along. Sometimes it's tough to remember all the information you get during an appointment; someone who goes with you may remember something you missed.
Prepare questions. Write a list of questions so you don't forget to ask something important.
Questions to Ask Your Doctor
What's the most likely cause of my symptoms?
What kinds of tests do I need?
How long might my condition last?
What treatments are available, and what do you recommend for me?
I have other health conditions — how can I best manage these conditions together?
Should I see a specialist?
Where can I find out more information, and what websites do you recommend?
What to Expect From Your Doctor
You may be asked:
What symptoms have you noticed, and how painful or distressing are they?
Are you still having periods?
Are you having any spotting in menopause?
Are you sexually active?
Have you been treated for cancer?
Do you use scented soap, bubble bath products, a douche, or hygiene spray?
What medicines, vitamins, or other supplements do you take?
Frequently Asked Questions About Vaginal Atrophy
What is vaginal atrophy?
Vaginal atrophy is the older medical term for thinning and drying of the vagina's inner lining, usually after menopause. These changes are now considered part of genitourinary syndrome of menopause (GSM), a group of symptoms affecting the genitals and lower urinary tract that happens when the body has less estrogen.
What causes vaginal atrophy?
Lower estrogen causes the tissues in the vagina to become thinner, drier, less elastic and more fragile. Estrogen can drop after menopause, during perimenopause, after surgery to remove both ovaries, during breastfeeding, from some birth control pills, after chemotherapy or pelvic radiation, or as a side effect of hormonal breast cancer treatment.
What are the symptoms?
Symptoms can include dryness, burning or itching in the vagina; unusual thin, watery, sticky, yellow or gray discharge; frequent or urgent urination; urinary incontinence; more frequent infections; pain during sex; light bleeding after sex; and shortening and tightening of the vaginal canal.
Can vaginal atrophy be prevented?
Regular sexual activity, with or without a partner, may help prevent GSM because it increases blood flow to the vagina and keeps tissues healthy. Smoking, having no vaginal births, and having no sexual activity may raise the risk.
What treatments are available?
Treatment starts with over-the-counter vaginal moisturizers and lubricants. If symptoms persist, options include topical vaginal estrogen (cream, suppository, ring or tablet), ospemifene (Osphena), prasterone (Intrarosa), systemic estrogen, vaginal dilators, and topical lidocaine.
Is vaginal estrogen safe if I've had breast cancer?
Low-dose vaginal estrogen may be an option if hormone-free treatments don't help, and your oncologist can discuss this with your healthcare professional — for most women there's minimal risk of breast cancer coming back with low-dose vaginal estrogen. Systemic estrogen therapy is generally not recommended, especially if your breast cancer was hormone-sensitive.
When should I see a doctor?
See a doctor for unexplained light spotting or bleeding, unusual vaginal discharge, burning or soreness, or painful sex that doesn't improve after trying a vaginal moisturizer or water- or silicone-based lubricant.
How is vaginal atrophy diagnosed?
A provider usually diagnoses it from your symptoms and a pelvic exam. Urine tests or other tests may be done to rule out infection or other causes.
Does vaginal atrophy go away on its own?
Usually not. Because it is caused by low estrogen, symptoms tend to continue or slowly worsen without treatment, but they often improve well with moisturizers, lubricants or prescription treatment.
How long does vaginal estrogen take to work?
Many people notice some relief within a few weeks, but it can take a few months to see the full benefit. Your provider will tell you how often to use it and when to follow up.
Conclusion
Vaginal atrophy may feel like a private struggle, but it is common, well understood, and very treatable. Three lessons stand out:
It has a new name — and a new understanding. What was once called vaginal atrophy or atrophic vaginitis is now recognized as genitourinary syndrome of menopause (GSM), a whole-body estrogen story affecting both the genitals and the lower urinary tract.
Embarrassment is the biggest barrier — not the condition. Many people suffer silently when simple treatments exist. Unexplained bleeding, unusual discharge, burning, or painful sex that outlasts lubricants all deserve a doctor's visit.
Relief comes in a ladder. From moisturizers and lubricants to topical estrogen, prescription pills, dilators, and pelvic floor therapy, there is an option for every level of symptoms — including safe paths for breast cancer survivors.
From the first dry, burning symptom through pelvic exams, estrogen drops, and all seven treatment steps, this guide covers the full picture of living comfortably after menopause. If you want to explore more women's health topics, start with our guide to understanding menopause.
Your Next Steps
Read a related guide — Learn how the menopause transition unfolds in our guide to understanding menopause.
Share your thoughts — Comment on this article with your questions or what worked for you.
Disclaimer: This article is for general informational purposes only and does not constitute medical advice. Always consult a qualified healthcare professional for diagnosis and treatment.
Related Reading
Hormone Therapy for Menopause: Benefits, Risks and Types explains the benefits and risks of menopause hormone therapy.
Painful Intercourse (Dyspareunia): Causes, Diagnosis, and Treatment Explained covers causes of painful sex and how it is treated.
Understanding Vaginal Dilators: A Guide to Restoring Comfort and Flexibility explains how vaginal dilators are used to ease tightness.
Perimenopause: Symptoms, Causes, and Treatments Explained describes the hormone changes leading up to menopause.
References
Mayo Clinic Staff. Vaginal atrophy - Symptoms & causes. Mayo Clinic. December 20, 2025. https://www.mayoclinic.org/diseases-conditions/vaginal-atrophy/symptoms-causes/syc-20352288
Mayo Clinic Staff. Vaginal atrophy - Diagnosis & treatment. Mayo Clinic. December 20, 2025. https://www.mayoclinic.org/diseases-conditions/vaginal-atrophy/diagnosis-treatment/drc-20352294
Mili N, et al. Genitourinary syndrome of menopause: a systematic review on prevalence and treatment. Menopause. 2021;28(6):706-716. PMID 33739315. https://doi.org/10.1097/GME.0000000000001752
Rahn DD, et al. Vaginal estrogen for genitourinary syndrome of menopause: a systematic review. Obstet Gynecol. 2014;124(6):1147-1156. PMID 25415166. https://doi.org/10.1097/AOG.0000000000000526
Danan ER, et al. Hormonal Treatments and Vaginal Moisturizers for Genitourinary Syndrome of Menopause: A Systematic Review. Ann Intern Med. 2024;177(10):1400-1414. PMID 39250810. https://doi.org/10.7326/ANNALS-24-00610
Beste ME, et al. Vaginal estrogen use in breast cancer survivors: a systematic review and meta-analysis of recurrence and mortality risks. Am J Obstet Gynecol. 2025;232(3):262-270.e1. PMID 39521301. https://doi.org/10.1016/j.ajog.2024.10.054
Santos GML, et al. Vaginal estrogen therapy for treatment of menopausal genitourinary syndrome among breast cancer survivors: a systematic review and meta-analysis. Rev Bras Ginecol Obstet. 2025;47. PMID 40673012. https://doi.org/10.61622/rbgo/2025rbgo46



Comments