Giant Cell Arteritis (Temporal Arteritis): Symptoms, Causes, Diagnosis & Treatment — Complete Guide

Updated: 2 days ago
Medically reviewed by Dr. Baraa Alnahhal, MD · Last reviewed: October 2026
Quick Answer
Giant cell arteritis is inflammation of the lining of the arteries, most often those in the temples, which is why it was called temporal arteritis. It causes headaches, scalp soreness, jaw pain with chewing and vision issues, and untreated it can lead to blindness. Early corticosteroid treatment usually relieves symptoms and may prevent vision loss, but relapses are common.
What the research says
Tocilizumab helped more patients stay in remission while using less prednisone. In a 1-year trial of 251 patients, sustained remission at week 52 occurred in 56% of those on weekly tocilizumab and 53% of those on every-other-week dosing, versus 14% and 18% in the two placebo-plus-prednisone-taper groups (P<0.001); the cumulative median prednisone dose was 1,862 mg with tocilizumab versus 3,296 mg and 3,818 mg with placebo. (Stone et al., N Engl J Med, 2017) [3]
An oral medicine, upadacitinib, also beat placebo. In a phase 3 trial (209 patients on 15 mg, 107 on 7.5 mg, and 112 on placebo), sustained remission at week 52 was 46.4% (95% CI 39.6 to 53.2) with the 15 mg dose versus 29.0% (95% CI 20.6 to 37.5) with placebo (P = 0.002); the 7.5 mg dose was not superior (41.1%), and no major adverse cardiovascular events occurred in the upadacitinib groups. (Blockmans et al., N Engl J Med, 2025) [4]
Temporal artery ultrasound is useful but cannot yet replace biopsy. A Cochrane review of 15 studies (617 people with giant cell arteritis among 1,479 participants) found a median sensitivity of 0.78 and a median specificity of 0.91 for the halo sign on temporal artery ultrasound; the evidence was of very low certainty, and the authors could draw no conclusion on whether ultrasound can replace biopsy. (Pouncey et al., Cochrane Database Syst Rev, 2024) [5]
At a Glance
Item | Summary |
What it is | Inflammation of the artery lining, mostly in the temples |
Also known as | Temporal arteritis (older name); a form of vasculitis |
Most common symptoms | New lasting temple headaches, scalp soreness, jaw pain when chewing |
Vision warning | Vision loss or double vision — mainly in people with jaw pain; sudden one-eye vision loss is an emergency |
Biggest risk factor | Age over 50 (most cases start between 70 and 80) |
Key complication | Blindness — usually sudden, painless, and lifelong |
Also monitored for | Aortic aneurysm (even years later) and stroke (uncommon) |
Best test | Temporal artery biopsy; supported by sed rate, CRP, and imaging |
Main treatment | High-dose corticosteroids (e.g., prednisone), started quickly |
Newer medicines | Tocilizumab (injection/IV) and upadacitinib (oral) — both lower steroid needs |
What Is Giant Cell Arteritis?
Giant cell arteritis is irritation and swelling, called inflammation, of the lining of the arteries. Arteries are the blood vessels that carry blood from the heart to other parts of the body. Most often, giant cell arteritis affects the arteries in the head, mainly those in the temples. For this reason, giant cell arteritis used to be called temporal arteritis.
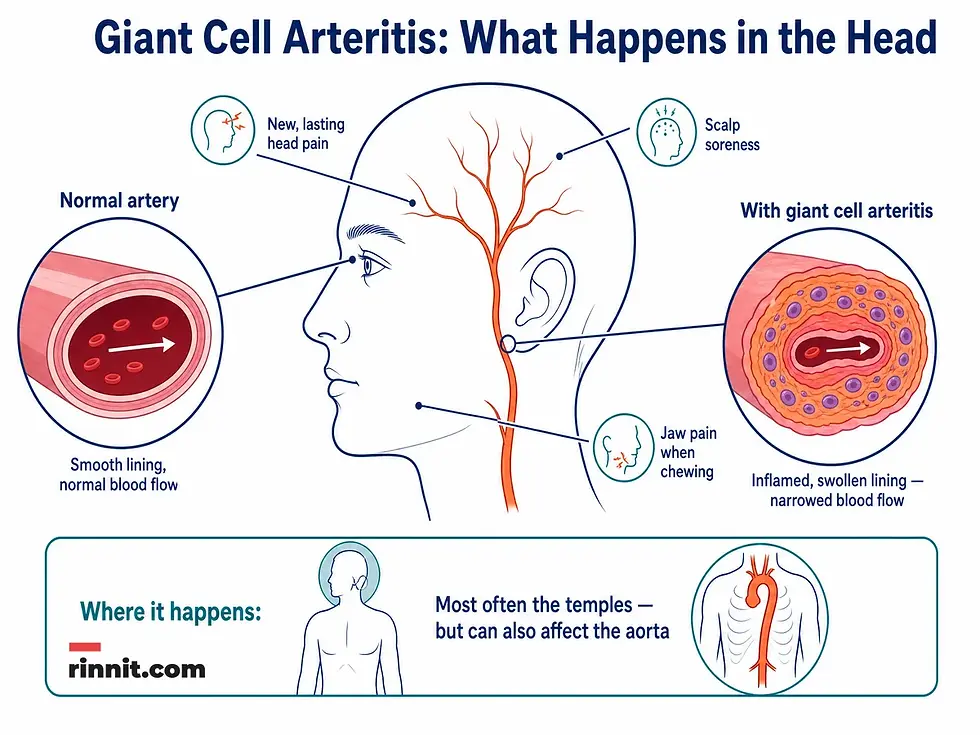
The condition often causes headaches, scalp soreness, jaw pain with chewing, and vision issues. If not treated, giant cell arteritis can lead to blindness. Early treatment with corticosteroid medicines most often relieves symptoms and might prevent vision loss.
Two things are important to understand about the road ahead. First, even with treatment, symptoms often return — this is called a relapse. Second, people with giant cell arteritis need regular checkups with their healthcare professionals: to treat the condition and to prevent the side effects of the corticosteroids themselves.
Symptoms of Giant Cell Arteritis
The most common symptoms of giant cell arteritis are headaches and tenderness in both temples or other areas of the scalp. These symptoms can be bad.
Symptoms of giant cell arteritis may include:
Symptom | What you notice |
New, lasting head pain | Most often in the temples |
Scalp soreness | Tenderness when touching the scalp |
Jaw pain when chewing | Pain that appears while eating |
Fever | An unexplained elevated temperature |
Tiredness | Feeling unusually worn out |
Weight loss | Losing weight without trying |
Vision loss or double vision | Mainly in people who also have jaw pain |
Sudden, lasting vision loss | Loss of vision in one eye |
The Polymyalgia Rheumatica Connection
Pain and stiffness in the neck, shoulders, or hips are common symptoms of a linked condition called polymyalgia rheumatica. About 40% to 50% of people with giant cell arteritis also have polymyalgia rheumatica. If you have stiffness in these areas along with a new headache, mention both to your provider.
When to See a Doctor
If you get a new, lasting headache or any of the symptoms listed above, see your healthcare professional right away. If you're diagnosed with giant cell arteritis, starting treatment quickly may help prevent vision loss.
Causes
It's not clear what causes arteries to become inflamed in giant cell arteritis. Experts believe it may involve the immune system attacking the artery walls by mistake. Certain genes and factors in the environment might raise your risk of the condition.

Risk Factors
Several factors can increase your risk of getting giant cell arteritis:
Risk factor | Detail |
Age | Giant cell arteritis affects adults, most often those older than 50. Most people get symptoms between the ages of 70 and 80. |
Sex assigned at birth | People assigned female at birth are about twice as likely to get the condition as people assigned male at birth. |
Race and ethnic background | Most common among white people in Northern Europe or those of Scandinavian descent. |
Polymyalgia rheumatica | Having this condition raises the risk of giant cell arteritis. |
Complications
Giant cell arteritis can cause serious complications:
Complication | What happens |
Blindness | The complication that causes the most worry. Less blood flow to the eyes can cause sudden, painless vision loss in one eye. Rarely, vision loss affects both eyes. Vision loss most often is lifelong. |
Aortic aneurysm | An aneurysm is a bulge that forms in a weakened blood vessel — most often in the aorta, the large artery running down the center of the chest and belly. An aortic aneurysm might burst, causing life-threatening bleeding inside the body. This can happen even years after diagnosis, so your healthcare professional may check your aorta with periodic imaging tests, such as an echocardiogram, CT, or MRI. |
Stroke | A complication of giant cell arteritis, but not common. |
How Giant Cell Arteritis Is Diagnosed
Giant cell arteritis can be hard to diagnose because its early symptoms are like those of other common conditions. Your healthcare professional tries to rule out other possible causes of your symptoms.
Besides asking about your symptoms and medical history, your provider does a physical exam and looks at the arteries around your temple, called the temporal arteries. Often, one or both arteries are tender, with a lower pulse and a hard, cordlike feel and look.
Blood Tests
Test | What it measures |
Erythrocyte sedimentation rate (sed rate) | How quickly red blood cells fall to the bottom of a tube of blood. A high sed rate may mean inflammation in your body. |
C-reactive protein (CRP) | A substance your liver makes when inflammation is present. Most people with giant cell arteritis have a high CRP. |
Imaging Tests
Imaging tests may help diagnose giant cell arteritis and check how well your treatment works:
Test | What it does |
Doppler ultrasound | Uses sound waves to make images of blood flowing through blood vessels; checks the temporal and other affected vessels. |
CT angiography (CTA) | A CT scan that uses dye to make detailed images of your blood vessels. Tell your provider ahead of time if you're allergic to iodine contrast dye or your kidneys don't work well. |
Magnetic resonance angiography (MRA) | An MRI that uses dye and a magnetic field to make detailed vessel images. Tell your team if you fear small spaces (claustrophobia — the test takes place in a tube-shaped machine) or have metal in your body. |
PET (positron emission tomography) | Checks for giant cell arteritis in large arteries, such as the aorta. Uses a sugar tracer liquid with a tiny amount of radioactive substance to show areas of inflammation in larger blood vessels. |
The Biopsy: Best Confirmation
The best way to confirm a diagnosis is by taking a small sample of the temporal artery and sending it to a lab for tissue study. It's an outpatient procedure done with local numbing medicine — most often safe, with little pain or scarring.
For people with giant cell arteritis, the artery often has a group of cells that are larger than usual. These giant cells give the condition its name.
A few things to know about biopsy results: it's possible to have giant cell arteritis and still get a negative biopsy result. If the results aren't clear, your provider might suggest a second biopsy on the other side of your head. An ultrasound of the temporal arteries can also check for giant cell arteritis, and some people have ultrasound instead of a biopsy.
Treatment of Giant Cell Arteritis
The main treatment for giant cell arteritis has been high doses of a corticosteroid medicine such as prednisone. Because fast treatment is needed to prevent vision loss, your provider may have you start the medicine even before a biopsy confirms the diagnosis if giant cell arteritis is likely.
Here's what the treatment journey typically looks like:
You're likely to feel better within a few days of starting treatment.
If you had visual loss before starting corticosteroids, your vision most likely won't improve — another reason speed matters.
You may need the medicine for months or sometimes longer. After the first month, the dosage is lowered little by little. The goal is the least amount of corticosteroid that manages the condition.
Some symptoms may return as the dosage is lowered (a flare-up). This is also when many people develop symptoms of polymyalgia rheumatica. Treating flare-ups may involve raising the corticosteroid dose.
Corticosteroid Side Effects
Corticosteroids can cause serious side effects, including bone thinning (osteoporosis), high blood pressure, and muscle weakness. Your healthcare professional may watch your bone density and prescribe calcium and vitamin D supplements or other medicines to help prevent bone loss.
Newer Medicines That Lower the Steroid Dose
Medicine | How it's taken | Key points |
Tocilizumab (Actemra) | A shot under the skin or through an arm vein | Often lowers the amount of corticosteroid needed. Side effects include raising the risk of infections. People with a history of diverticulitis (inflamed or infected pouches in the large bowel wall) shouldn't take it. |
Upadacitinib (Rinvoq) | Taken by mouth | A newer medicine that often lowers the corticosteroid dose needed. Side effects include raising the risk of infections and shingles, and possibly a higher risk of heart attack and blood clots. |
Both medicines lower the risk of flare-ups of giant cell arteritis. Your healthcare professional guides you to the best treatment for you, and researchers are studying other medicines as well.
Lifestyle Changes and Home Remedies
The following may help you manage giant cell arteritis and cope with the side effects of your medicine:
Eat a healthy diet. Eating well can help prevent thinning bones, high blood pressure, and diabetes. Focus on fresh fruits and vegetables, whole grains, and lean meats and fish. Limit salt, sugar, and alcohol.
Exercise regularly. Regular aerobic exercise, such as walking, can help prevent bone loss, high blood pressure, and diabetes — and it helps your heart and lungs. Many people find that exercise improves their mood and overall sense of well-being. If you're not used to exercising, start slowly and build up over time; your healthcare professional can help you plan an exercise program.
Get checkups. See your healthcare professional regularly to check for side effects of treatment and for complications.
Coping and Support
Learning everything you can about giant cell arteritis and its treatment can help you feel more in control of your condition. Your healthcare team can answer your questions, and online support groups may also be helpful.
Know the side effects of the medicines you take, and tell your healthcare professional about any changes to your health. Because the condition and its treatment are managed over months or years, a small support circle — family, friends, or an online community — makes a real difference in staying on track with checkups and bone-protection habits.
Preparing for Your Appointment
You might start by seeing your main healthcare professional, who may send you to one or more specialists:
Specialist | Why you'd see them |
Ophthalmologist | An eye specialist, for visual symptoms |
Neurologist | A brain and nervous system specialist, for headaches |
Rheumatologist | A specialist in diseases of the joints, bones, and muscles |
What You Can Do
When you make the appointment, ask if there's anything you need to do beforehand — for some tests used to diagnose giant cell arteritis, you might need to follow special instructions. Then make a list of:
Your symptoms and when they began.
Key personal information, including any major stresses or recent life changes.
All medicines, vitamins, and other supplements you take, including dosages.
Questions to ask your healthcare professional.
Take a friend or family member with you to help you remember the information you get.
Questions to Ask Your Healthcare Professional
What's the most likely cause of my symptoms?
What are other possible causes?
What tests do I need?
What treatments are there?
Will giant cell arteritis come back?
I have other health conditions — how can I best manage them together?
Do I need to change my diet or take supplements?
Do you have brochures or other information that I can have? What websites do you suggest?
Be sure to ask all the questions you have.
What Your Provider Will Likely Ask
Do you always have symptoms, or do they come and go?
How bad are your symptoms?
What, if anything, seems to make your symptoms better?
What, if anything, seems to make your symptoms worse?
What You Can Do in the Meantime
Ask your healthcare professional if taking a pain reliever such as acetaminophen (Tylenol), ibuprofen (Advil, Motrin IB), or naproxen sodium (Aleve) might help ease head pain or tenderness while you wait.
FAQ: Giant Cell Arteritis
What is giant cell arteritis?
Giant cell arteritis is irritation and swelling (inflammation) of the lining of the arteries. It most often affects the arteries in the head, mainly those in the temples — which is why it used to be called temporal arteritis. Untreated, it can lead to blindness.
What does giant cell arteritis feel like?
The most common symptoms are new, lasting headaches and tenderness in both temples or other areas of the scalp. Other symptoms include jaw pain when chewing, fever, tiredness, weight loss, and vision loss or double vision — especially in people who also have jaw pain.
Why is it called “giant cell” arteritis?
During diagnosis, a small sample of the temporal artery is examined in a lab. In people with giant cell arteritis, the artery often contains a group of cells that are larger than usual — these “giant cells” give the condition its name.
Can giant cell arteritis cause blindness?
Yes — blindness is the complication that causes the most worry. Reduced blood flow to the eyes can cause sudden, painless vision loss in one eye (rarely both). Vision loss most often is lifelong, which is why new, lasting temple headaches should be evaluated right away.
Who is at risk of giant cell arteritis?
The condition affects adults over 50, with most cases starting between 70 and 80. Women are about twice as likely as men to develop it, it's most common among white people of Northern European or Scandinavian descent, and having polymyalgia rheumatica raises the risk — 40% to 50% of people with giant cell arteritis have that condition too.
How is it diagnosed?
Diagnosis includes a physical exam of the tender, hard, cordlike temporal arteries; blood tests (sed rate and CRP, which both rise with inflammation); imaging such as Doppler ultrasound, CT angiography, MRA, or PET; and a temporal artery biopsy, which is the best way to confirm the diagnosis.
How is giant cell arteritis treated?
The main treatment is high doses of corticosteroids such as prednisone — sometimes started even before biopsy results return, because fast treatment protects vision. Symptoms often improve within days, but treatment lasts months or longer. Newer medicines, tocilizumab (injection/IV) and upadacitinib (oral), often reduce the steroid dose needed and lower flare-up risk.
Can giant cell arteritis come back?
Yes. Even with treatment, symptoms often return — a pattern called relapse. Flare-ups frequently appear as the corticosteroid dose is lowered, and they may be treated by raising the dose again. That's why regular, long-term checkups are part of managing this condition.
Conclusion
Giant cell arteritis is one of those conditions where speed truly saves sight. It is an inflammation of the artery lining — mostly in the temples — that produces distinctive warning signs: new, lasting temple headaches, a sore scalp, jaw pain when chewing, and vision changes that may arrive suddenly and without pain. Left untreated, it can cause lifelong blindness, an aortic aneurysm years down the road, or (less commonly) a stroke. This guide has covered the symptoms and their link to polymyalgia rheumatica, the four risk factors, the full diagnostic toolkit from sed rate to temporal artery biopsy, and the treatment path from high-dose corticosteroids to newer steroid-sparing medicines. The takeaway is simple: if you're over 50 and a new, persistent temple headache shows up — especially with jaw pain or any vision change — don't wait it out. See your healthcare professional right away.
Explore more condition guides on rinnit.com, including our aortic aneurysm guide.
Disclaimer: This article is for general informational purposes only and does not constitute medical advice. Always consult a qualified healthcare professional for diagnosis and treatment of any health condition. Never disregard professional medical advice or delay seeking it because of something you have read here.
Related Reading
ESR (Sed Rate) Test: What It Measures, Normal Range by Age and What High Results Mean explains the blood test used to check for inflammation.
References
Mayo Clinic Staff. Giant cell arteritis - Symptoms and causes. Mayo Clinic. June 2, 2026. https://www.mayoclinic.org/diseases-conditions/giant-cell-arteritis/symptoms-causes/syc-20372758
Mayo Clinic Staff. Giant cell arteritis - Diagnosis and treatment. Mayo Clinic. June 2, 2026. https://www.mayoclinic.org/diseases-conditions/giant-cell-arteritis/diagnosis-treatment/drc-20372764
Stone JH, et al. Trial of Tocilizumab in Giant-Cell Arteritis. N Engl J Med. 2017;377(4):317-328. PMID 28745999. https://doi.org/10.1056/NEJMoa1613849
Blockmans D, et al. A Phase 3 Trial of Upadacitinib for Giant-Cell Arteritis. N Engl J Med. 2025;392(20):2013-2024. PMID 40174237. https://doi.org/10.1056/NEJMoa2413449
Pouncey AL, et al. Halo sign on temporal artery ultrasound versus temporal artery biopsy for giant cell arteritis. Cochrane Database Syst Rev. 2024;2(2):CD013199. PMID 38323659. https://doi.org/10.1002/14651858.CD013199.pub2



Comments