Understanding Persistent Postural-Perceptual Dizziness (PPPD)

Updated: Nov 11
Medically reviewed by Dr. Baraa Alnahhal, MD · Last reviewed: October 2026
Quick Answer: What is persistent postural-perceptual dizziness (PPPD)?
Persistent postural-perceptual dizziness (PPPD) is a chronic condition causing frequent swaying or rocking sensations, usually following a balance-related event such as vertigo or concussion [1]. Unlike vertigo, it does not involve spinning, and symptoms worsen with standing or intense visual input [1]. Management includes vestibular rehabilitation, talk therapy to ease hyperfocus and medications to reduce anxiety [1].
What the research says
Vestibular rehabilitation reduces dizziness handicap. A meta-analysis of 8 studies found that vestibular rehabilitation therapy improved Dizziness Handicap Inventory scores by about 22 points compared with control (Li et al., Front Neurol, 2025) [2].
Antidepressants may help, but evidence is limited. A review of 13 studies (807 participants) reported response rates of 55% to 84% with antidepressants, though up to 25% could not tolerate treatment and most studies were low quality (Bukovsky et al., J Vestib Res, 2026) [3].
Persistent Postural-Perceptual Dizziness (PPPD) is a relatively new clinical diagnosis, first defined by experts in 2017 [1]. It represents a functional balance disorder where the brain and the balance system—including the eyes, inner ears, and muscles—stop working in sync [1]. While the individual components of the system remain healthy, the brain becomes hyperaware of balance signals, leading to a persistent feeling of being off-balance.
Unlike many other vestibular disorders, PPPD does not cause a spinning sensation [1]. Instead, those affected often describe feeling like they are on a rocking boat or swaying. This sensation is most prominent when the individual is upright or in settings with significant visual activity, such as a crowded grocery store or when scrolling through a digital device [1].
What are the core symptoms of persistent postural-perceptual dizziness (PPPD)?
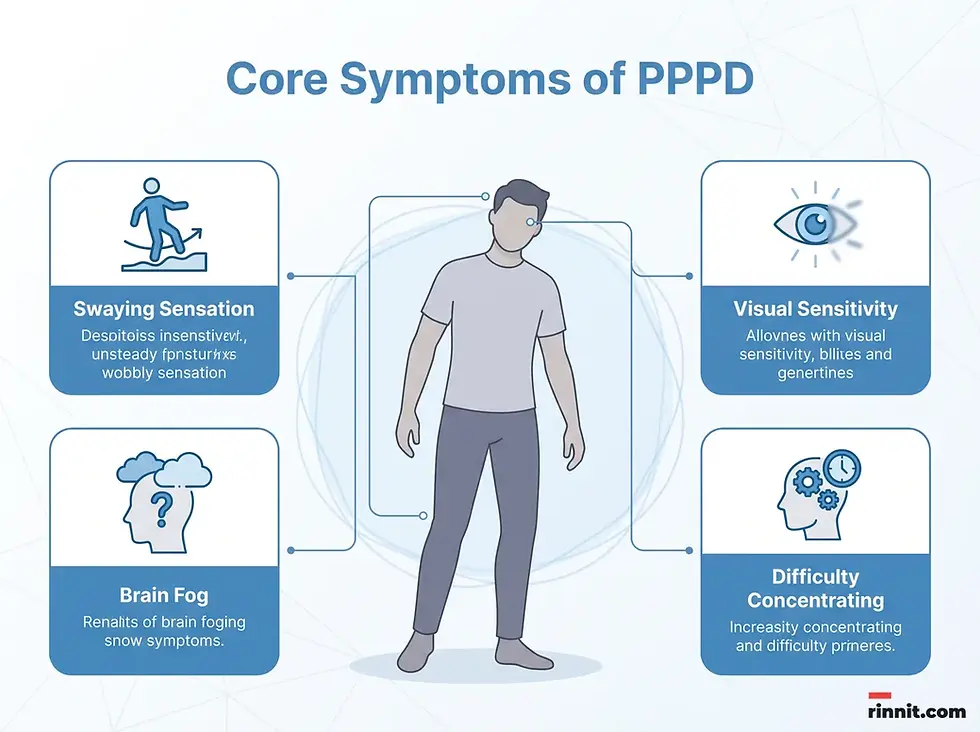
The primary indicator of PPPD is dizziness or unsteadiness that occurs more days than not for at least three consecutive months [1]. This dizziness can fluctuate throughout the day, often intensifying as the day progresses [1]. It is a persistent state rather than a series of isolated episodes.
Beyond the physical sensation of swaying, individuals may experience cognitive and sensory symptoms. These include “brain fog,” difficulty maintaining concentration, and a sense of being disconnected from one’s body or surroundings [1]. Short-term memory issues are also frequently reported [1], reflecting the mental strain of the brain constantly over-processing balance information.
What triggers PPPD and who is at risk?
PPPD typically develops following an acute event that disrupts the balance system [1]. Once the initial trigger passes, the brain remains in a state of high alert, failing to return to its normal, automatic processing of balance.
Primary Triggers
Acute vertigo [1]: Sudden episodes of spinning.
Head injuries [1]: Such as concussions or mild traumatic brain injuries.
Vestibular migraine [1]: Dizziness associated with migraine activity.
Panic attacks [1]: Intense episodes of anxiety that include physical symptoms.
Ménière’s disease [1]: A chronic inner ear condition.
Risk Profiles
Gender: Women are approximately four times more likely to develop PPPD than men [1].
History: A prior history of vestibular disorders or mood conditions increases risk [1].
Personality: Introverted individuals may be more prone to the hyperfocus required for PPPD [1].
Mood: Existing anxiety or depression can contribute to the development of the condition [1].
What are the diagnostic criteria for PPPD?
Diagnosing PPPD is often a process of exclusion and symptom matching because standard vestibular tests frequently return normal results [1]. Since there is no physical damage to the inner ear or brain, the diagnosis relies on a specific set of clinical criteria.
To receive a diagnosis, a patient must have experienced unsteadiness or non-spinning dizziness for most days over a three-month period. These symptoms must be triggered by a prior event and worsened by upright postures or complex visual stimuli. Furthermore, the symptoms must significantly interfere with daily life, and no other medical condition should better explain the presentation [1].

How is persistent postural-perceptual dizziness (PPPD) treated and managed?
PPPD has no definitive cure, but vestibular rehabilitation therapy, cognitive behavioral therapy and medications such as SSRIs or SNRIs can help retrain the brain and reduce symptoms [1]. A multi-modal approach is often most effective for achieving long-term stability.
Vestibular Rehabilitation Therapy (VRT)
VRT is a specialized form of physical therapy designed to retrain the balance system [1]. It involves exercises that help the brain become less sensitive to the signals that cause dizziness. Over time, these exercises can reduce the frequency and intensity of swaying sensations.
Cognitive Behavioral Therapy (CBT)
Talk therapy, specifically CBT, is used to address the hyperfocus and anxiety that often accompany PPPD. By reducing the brain’s hyperawareness of balance, patients can feel more comfortable in challenging environments. CBT also helps break the feedback loop between dizziness and anxiety.
Medication
Providers may prescribe Selective Serotonin Reuptake Inhibitors (SSRIs) or Serotonin-Norepinephrine Reuptake Inhibitors (SNRIs) [1]. These medications are not just for mood; they can help dampen the brain’s hyper-responsiveness to balance triggers, making other therapies more effective.
Vestibular rehab: Retrain the balance system and reduce sensitivity.
CBT: Ease anxiety and reduce hyperfocus on balance signals.
Medication: Balance brain chemistry to lower hyper-responsiveness.

How can people live well with PPPD?
Managing this condition requires significant patience and self-compassion. Because it is a functional disorder, patients may sometimes be told their symptoms are “all in their head.” However, PPPD is a recognized medical condition with real, disruptive effects on daily life.
Safety is a primary concern, particularly regarding activities like driving. Some individuals may find that the motion of a vehicle or the visual input of the road makes driving unsafe or unbearable [1]. It is essential to consult with a healthcare provider to determine when it is safe to operate a vehicle, especially during the early stages of treatment.
Conclusion
Persistent Postural-Perceptual Dizziness is a complex balance disorder that can significantly impact an individual’s independence and mental well-being. By recognizing the triggers and seeking early intervention through specialized therapies and medication, many people can regain their stability. If you are experiencing chronic dizziness, speak with a specialist to discuss a personalized management plan.
Ready to take the next step toward stability? Consult with a vestibular specialist today to explore your treatment options.
Frequently Asked Questions (FAQ)
Is PPPD the same as vertigo?
No. Vertigo involves a spinning sensation, whereas PPPD is characterized by swaying, rocking, or unsteadiness without spinning [1].
How long does PPPD last?
PPPD is a chronic condition that lasts at least three months, but for many, it can be a lifelong issue [1] that requires ongoing management.
Can anxiety cause PPPD?
Anxiety does not directly cause PPPD, but having an anxiety disorder can increase your risk of developing it after a balance-related trigger [1].
Why do my symptoms get worse in grocery stores?
Grocery stores provide intense visual information (many items, bright lights, movement), which triggers the brain’s hyper-responsiveness in PPPD.
Can children develop PPPD?
While most common in adults, especially women, any individual who experiences a balance-triggering event can potentially develop PPPD.
Is there a specific test for PPPD?
There is no single physical test. Diagnosis is based on clinical criteria and the patient’s history of symptoms and triggers [1].
Does medication cure PPPD?
Medication does not cure the condition [1], but it can help manage the symptoms and make physical therapy more effective.
Is PPPD a permanent condition?
PPPD is often considered lifelong [1], but many people experience significant relief and can lead normal lives with proper treatment.
Can head injuries lead to PPPD?
Yes, concussions and other head injuries are common triggers [1] that can lead to the development of chronic dizziness.
Should I avoid movement if I feel dizzy?
No. Avoiding movement can actually make PPPD worse. Controlled movement through vestibular rehab is a key part of recovery.
Can I drive with PPPD?
This depends on the severity of your symptoms. You should consult your doctor to ensure it is safe for you to drive.
What is vestibular rehabilitation?
Vestibular rehabilitation is a specialized physical therapy that uses specific exercises to help the brain and balance system work together again.
Why are women more likely to have PPPD?
Research is ongoing, but statistics show women are four times more likely to be diagnosed with the condition than men [1].
Can PPPD be misdiagnosed?
Yes, because it is a newer diagnosis and tests often appear normal, it can sometimes be mistaken for pure anxiety or other balance issues.
What should I do if I suspect I have PPPD?
You should reach out to a healthcare provider, preferably one specializing in vestibular or balance disorders, for a formal evaluation.
Medical disclaimer: This content is for informational purposes only and does not constitute medical advice. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition.
Related Reading
Vestibular Migraine: Symptoms, Causes, and Management explains how migraine can cause vertigo and lasting dizziness.
Vestibular Rehabilitation Therapy: Managing Dizziness and Balance describes the balance exercises used to retrain the brain after dizziness.
Vertigo (BPPV): Symptoms, Causes, and How It Is Treated explains the common inner-ear cause of spinning vertigo and its treatment.
Vestibular Neuritis: Causes, Symptoms, and Recovery covers the inner-ear nerve inflammation that often comes before PPPD.
References
Cleveland Clinic. Persistent Postural-Perceptual Dizziness. Cleveland Clinic. August 13, 2025. https://my.clevelandclinic.org/health/diseases/persistent-postural-perceptual-dizziness
Li Y, et al. Effect of vestibular rehabilitation therapy in patients with persistent postural perceptual dizziness: a systematic review and meta-analysis. Front Neurol. 2025;16:1599201. PMID 41069431. https://doi.org/10.3389/fneur.2025.1599201
Bukovsky D, et al. Evaluating the effect of antidepressants for persistent postural-perceptual dizziness: A systematic review. J Vestib Res. 2026. PMID 42678338. https://doi.org/10.1177/09574271261468395



Comments