Understanding Megaureter: Causes, Types, and Care Pathways

Updated: Nov 11
Medically reviewed by Dr. Baraa Alnahhal, MD · Last reviewed: October 2026
Quick Answer
Megaureter is a ureter that is wider than normal, exceeding 3/8 of an inch. It is usually congenital and is four times more common in males. It is often symptom-free but can lead to urinary tract infections or kidney damage if untreated. Treatment ranges from watchful waiting with regular ultrasounds to surgery for more severe cases.
What the research says
Many megaureters in babies get better on their own. In 60 newborns with 72 primary megaureters followed for up to 15 years, 52.8% resolved without surgery, 25% stayed widened, and 22.2% needed an operation. Poor drainage on a kidney scan, severe swelling and a ureter wider than 15 mm predicted the need for surgery (Arena et al., Scandinavian Journal of Urology and Nephrology, 2012). [3]
Balloon dilation is a less invasive option. A review of 13 studies found that high-pressure balloon dilation of an obstructed megaureter succeeded in 71% of children after one procedure and 79% after two, shrinking the ureter from about 15.8 mm to 8.0 mm. Complications occurred in 33%, but none were severe (Ripatti et al., BMC Urology, 2023). [4]
What is a Megaureter?
The urinary system relies on two thin tubes called ureters to transport urine from the kidneys to the bladder. In a typical developing child, these tubes are approximately 1/4-inch wide. A megaureter occurs when one or both of these tubes become enlarged, reaching a width of 3/8-inch or greater.
Most megaureters are congenital, meaning they are present at birth and develop during fetal growth. While the condition is relatively rare, it is notably more prevalent in males, occurring about four times as often as in females. If not properly managed, a severe megaureter can lead to complications within the child's urinary system, potentially impacting long-term kidney health.
What are the types of megaureter?
Megaureters are classified based on the underlying cause of the enlargement. Understanding the specific type is crucial for determining the appropriate management strategy.
Refluxing Megaureter: Caused by vesicoureteral reflux, where urine flows backward from the bladder into the ureter.
Primary Obstructed Megaureter: Occurs when the ureter is too narrow at the point where it enters the bladder, creating a blockage.
Primary Non-Obstructed, Non-Refluxing: An enlarged ureter that does not exhibit backflow or a clear physical blockage.
Refluxing Obstructed Megaureter: A rare combination where both backflow and a physical obstruction are present.
Secondary Megaureter: Enlargement resulting from other conditions, such as urethral blockages or neurogenic bladder.

What are the symptoms and warning signs of megaureter?
In many instances, a megaureter does not produce noticeable symptoms and is first identified during routine prenatal ultrasounds. However, when symptoms do manifest in infants or children, they often relate to urinary tract issues.
Common signs that may indicate a megaureter include:
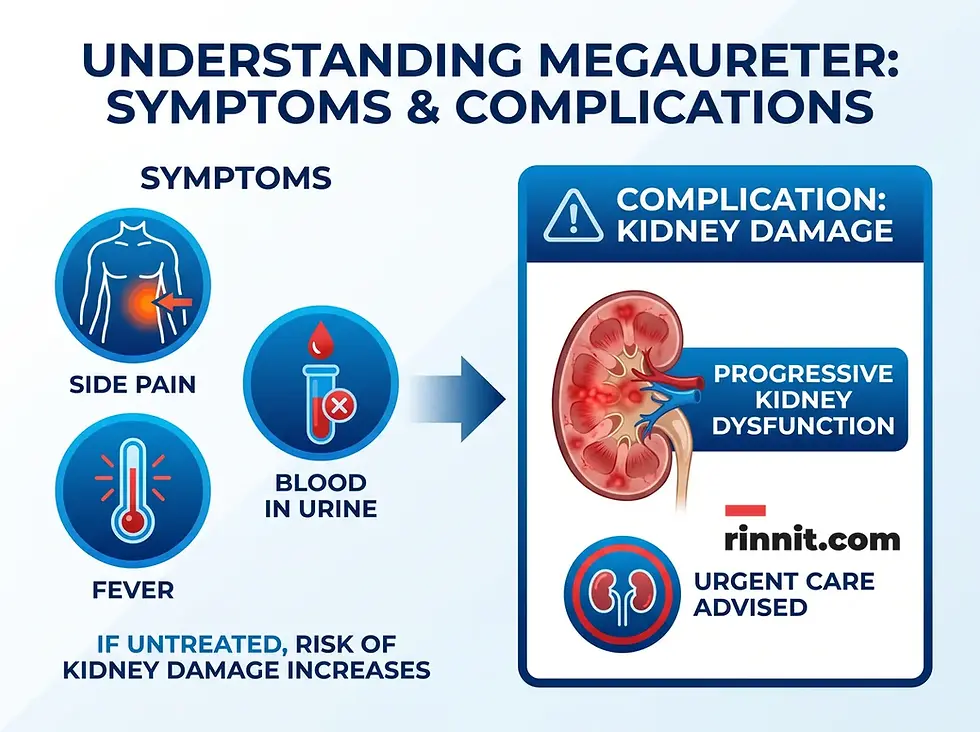
Localized Pain: Discomfort or pain in the side (flank area).
Urinary Changes: The presence of blood in the urine (hematuria) or a loss of bladder control.
Signs of Infection: Recurrent urinary tract infections (UTIs) accompanied by fever. To learn more about how these infections develop and are treated, see our guide to urinary tract infections.
What causes megaureter, and how does it develop?
Megaureters primarily develop during fetal growth. In some cases, a section of the ureter develops stiff, fibrous tissue instead of the flexible muscle tissue required for normal function. This prevents the wavelike contractions, known as peristalsis, that move urine toward the bladder.
Other causes include physical blockages, such as a ureterocele, which prevents urine from entering the bladder correctly. This leads to a backup of urine toward the kidney, causing the ureter to dilate and widen over time.
How is megaureter diagnosed?
The diagnostic journey often begins before birth with a prenatal ultrasound. This imaging technique uses sound waves to visualize the developing structures of the fetus's kidneys, ureters, and bladder.
If a megaureter is suspected after birth, healthcare providers may utilize several tests to confirm the diagnosis and assess kidney function:
Voiding Cystourethrogram (VCUG): A specialized X-ray that uses contrast dye to check for urine backflow.
Renal Ultrasound and Scan: Imaging to monitor kidney growth and check for blockages using radioactive tracers.
Laboratory Tests: Urinalysis to check for infections and electrolyte panels to monitor how well the kidneys are filtering the blood.
How is megaureter managed and treated?
The treatment for megaureter is highly individualized, depending on the child's age, the severity of the enlargement, and overall health. Many children do not require immediate surgery and will eventually outgrow the condition.
The Watch-and-Wait Approach
For many patients, a conservative "watch-and-wait" strategy is employed. This includes:
Regular Monitoring: Frequent ultrasounds to ensure the kidneys are developing normally.
Preventative Care: Low-dose antibiotics may be prescribed to reduce the risk of recurring UTIs.
Surgical Intervention
Surgery becomes necessary if the megaureter increases in size, causes repeated infections, or begins to impair kidney function. Common surgical options include pyeloplasty, which removes the blocked section of the ureter, or a temporary ureterostomy to redirect urine flow while the system heals.

What is the outlook and long-term care for megaureter?
The long-term outlook for children with megaureter is generally very positive. Most cases identified prenatally improve gradually without the need for surgery. For those who do require surgical correction, recovery typically takes a few weeks, and most children go on to have normal urinary and kidney function. Regular follow-up care is essential to ensure continued health and to catch any potential complications early.
Frequently Asked Questions
1. What is a megaureter?
A megaureter is a congenital condition where the ureter, the tube connecting the kidney to the bladder, is wider than normal.
2. How wide is a megaureter?
A ureter is considered a megaureter if it is wider than 3/8 of an inch.
3. Is this condition common?
Megaureter is considered relatively rare and is most often found during fetal development.
4. Why is it more common in boys?
Medical research shows it occurs about four times more often in males, though the exact reason is still being studied.
5. Can it be found before the baby is born?
Yes, most megaureters are discovered during routine prenatal ultrasounds.
6. What are the main types?
The two primary types are refluxing (urine flows backward) and obstructed (a blockage stops urine flow).
7. What symptoms should I look for?
Symptoms can include side pain, blood in the urine, fever, and frequent urinary tract infections.
8. Does every child need surgery?
No. Many children outgrow the condition and only require regular monitoring and antibiotics.
9. What is a VCUG test?
A VCUG test is a specialized X-ray that uses dye to see if urine is flowing backward from the bladder to the kidneys.
10. How do antibiotics help?
Antibiotics are often used at low doses to prevent urinary tract infections while waiting for the child to outgrow the condition.
11. When is surgery necessary?
Surgery is usually recommended if the ureter continues to widen, causes repeated infections, or affects kidney health.
12. What is pyeloplasty?
Pyeloplasty is a surgical procedure to remove a blockage in the ureter and reconnect it to ensure proper urine flow.
13. How long is the recovery after surgery?
Most children recover within a few weeks following surgical correction of a megaureter.
14. Can megaureter cause kidney damage?
If left untreated, severe cases can lead to infections and potential damage to the kidneys.
15. Will my child have normal kidney function?
With proper monitoring and treatment, the majority of children with megaureter have excellent long-term outcomes.
References
Mayo Clinic Staff. Ureteral obstruction - Symptoms and causes. Mayo Clinic. December 23, 2025. https://www.mayoclinic.org/diseases-conditions/ureteral-obstruction/symptoms-causes/syc-20354676
Mayo Clinic Staff. Ureteral obstruction - Diagnosis and treatment. Mayo Clinic. December 23, 2025. https://www.mayoclinic.org/diseases-conditions/ureteral-obstruction/diagnosis-treatment/drc-20354680
Arena S, et al. Long-term follow-up of neonatally diagnosed primary megaureter: rate and predictors of spontaneous resolution. Scand J Urol Nephrol. 2012;46(3):201-207. PMID 22397575. https://doi.org/10.3109/00365599.2012.662695
Ripatti L, et al. High-pressure balloon dilatation of primary obstructive megaureter in children: a systematic review. BMC Urol. 2023;23(1):30. PMID 36869342. https://doi.org/10.1186/s12894-023-01199-5
Medical disclaimer
Medical Disclaimer: The information provided in this article is for educational purposes only and should not be used as a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of a qualified healthcare provider with any questions you may have regarding a medical condition.



Comments