
Primary Biliary Cholangitis (PBC): Complete Guide to Symptoms, Causes, Diagnosis, and Treatment

Updated: 2 days ago
Medically reviewed by Dr. Baraa Alnahhal, MD · Last reviewed: September 2026
TL;DR
Primary biliary cholangitis (PBC) is a chronic autoimmune liver disease in which the immune system attacks the small and medium bile ducts in the liver. Trapped bile builds up (cholestasis) and gradually scars liver tissue, potentially leading to cirrhosis and liver failure. It most often affects middle-aged and older women, and more than half of people have no symptoms at diagnosis. Ursodiol is the first-line medicine; a liver transplant is the only known cure. See a doctor for severe, persistent itching or unexplained extreme tiredness.
Quick Answer
Primary biliary cholangitis (PBC) is an uncommon, long-term liver disease in which the body's immune system mistakenly attacks the bile ducts within the liver. This gradually decreases the flow of bile from the liver to the small intestine, and the buildup of bile damages and destroys liver tissues. It most often affects middle-aged and older women. The first-line medicine is ursodiol, and a liver transplant is the only treatment known to cure PBC, reserved for liver failure or severe complications. Make an appointment if you have severe, persistent itching with no obvious cause, or extreme tiredness that rest does not relieve.
What Is Primary Biliary Cholangitis?
Primary biliary cholangitis (PBC) is an uncommon, long-term disease of the liver in which the body's immune system mistakenly attacks bile ducts within the liver. This gradually decreases the flow of the digestive fluid bile from the liver to the small intestine, and the buildup of bile damages and destroys liver tissues.
The disease destroys the lining of the small- and medium-sized bile ducts that transport bile from the liver. Leaking bile and related disease activity damage liver tissues. If left untreated, PBC can lead to scarring of tissues in the liver and liver failure.
PBC most often affects middle-aged and older women. It was formerly called primary biliary cirrhosis — a name that was changed because most people are diagnosed long before cirrhosis ever develops.

Symptoms: Silent at Diagnosis for Many
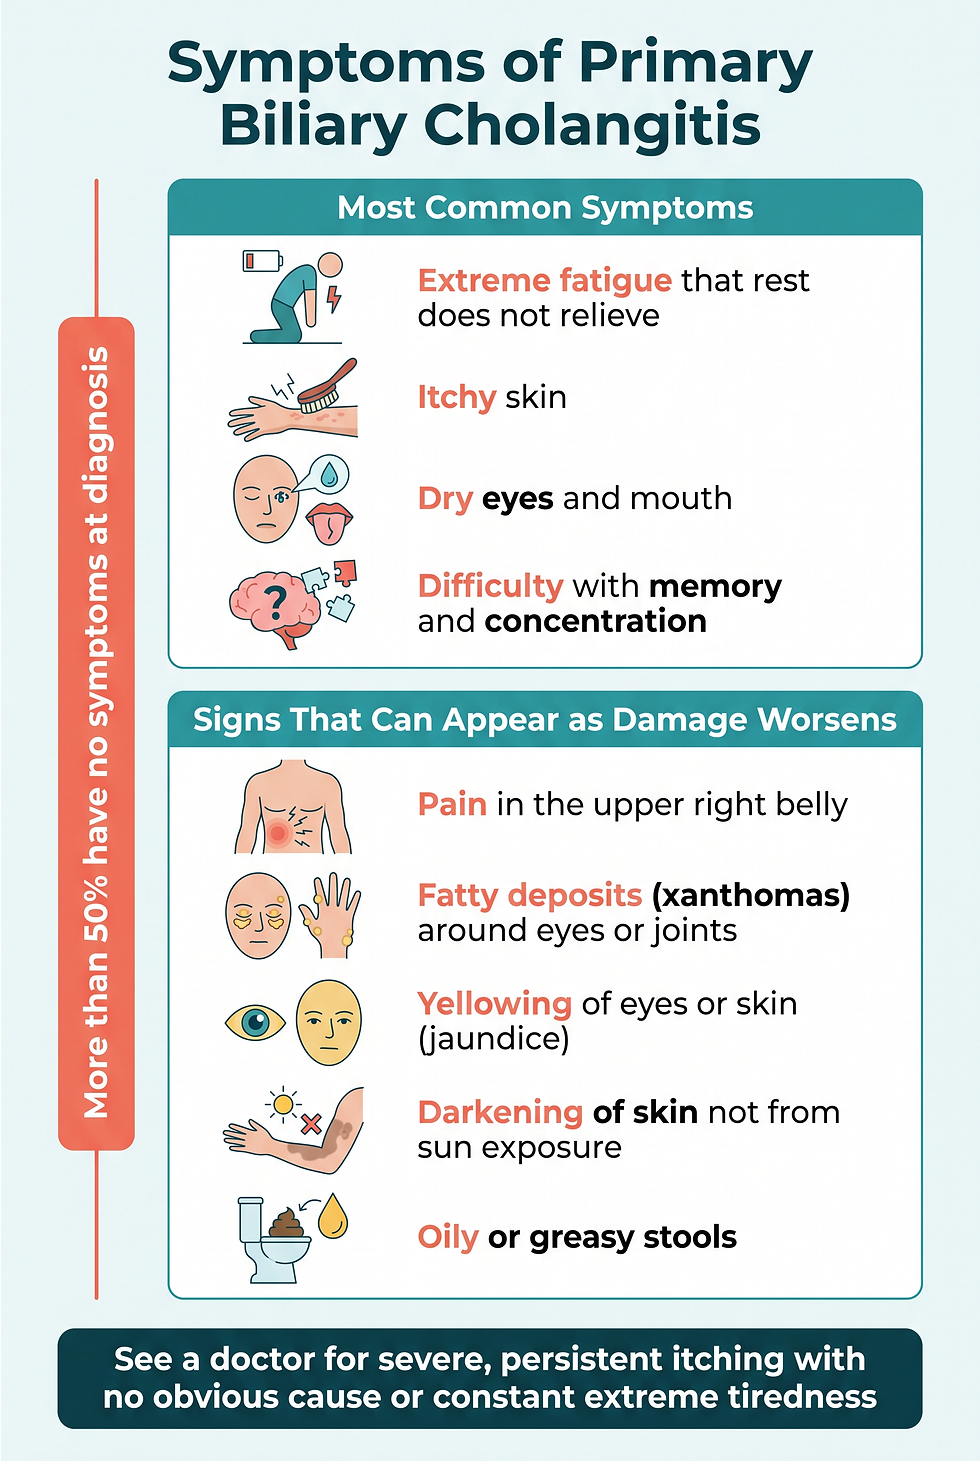
More than 50% of people with primary biliary cholangitis do not have symptoms when they get a diagnosis. But symptoms appear at some point as damage to the liver worsens.
The most common symptoms are fatigue, itchy skin, dry eyes and mouth, and difficulty with memory and concentration. Other signs and symptoms may include pain in the upper right belly, fatty deposits called xanthomas on the skin around the eyes or the creases of joints, yellowing of the whites of the eyes or skin called jaundice, darkening of the skin that is not related to sun exposure, and oily or greasy stools.
Symptom category | Signs to watch for |
|---|---|
Most common | Extreme fatigue; itchy skin; dry eyes and mouth; difficulty with memory and concentration |
As liver damage worsens | Upper right belly pain; xanthomas around eyes or joints; jaundice; unexplained skin darkening; oily or greasy stools |
When to See a Doctor
Two symptom patterns deserve prompt medical attention. Make an appointment if you have severe, persistent itching on much of your body with no obvious cause. Also see your health care professional if you feel extremely tired all the time, no matter how much rest you get.
Both of these are early, common signals of PBC — and because the disease is often silent at diagnosis, unexplained itching and fatigue should not be dismissed.
Causes: An Immune System Mistake
Primary biliary cholangitis is an autoimmune disease. This means the body's immune system attacks its own tissues as if it were fighting a disease.
Usually, certain types of white blood cells called lymphocytes find and attack germs or other foreign substances. In PBC, lymphocytes mistakenly target healthy cells lining the small- and medium-sized bile ducts in the liver. The immune system also makes disease-fighting proteins, called antibodies, that attack these healthy cells.
Bile ducts in the liver are gradually damaged and destroyed, causing bile to build up in the liver — a condition called cholestasis. Leaking bile, inflammation, and other immune system activity cause damage and scarring of liver tissues, called fibrosis, which leads to poor liver function. Eventually, fibrosis can lead to severe, permanent scarring, called cirrhosis.
Disease process | What it means |
|---|---|
Autoimmune attack | Lymphocytes and antibodies target the lining of small and medium bile ducts |
Cholestasis | Bile builds up in the liver as ducts are damaged |
Fibrosis | Scarring of liver tissues from leaking bile and inflammation |
Cirrhosis | Severe, permanent scarring; a late-stage outcome if untreated |
Potential Triggers and Coexisting Conditions
It is not clear what triggers this autoimmune disease. Research suggests several potential triggers that may lead to PBC in people with a genetic risk of the disease. These may include infections of the urinary tract or digestive tract, cigarette smoking, chemicals including chemicals in some cosmetics, and environmental pollution.
People with PBC often have another autoimmune disease. These may include thyroid disease, rheumatoid arthritis, Sjogren syndrome (which causes dry eyes and mouth), and inflammatory bowel disease.
Risk Factors
The following factors may increase your risk of primary biliary cholangitis:
Risk factor | Detail |
|---|---|
Sex assigned at birth | Most people with the disease are women |
Age | Most often affects middle-aged and older adults |
Genetics | More likely if a family member has or had it |
Geography | Most common among people in North America and Northern Europe |
Complications
As liver damage worsens, primary biliary cholangitis can cause serious health problems.
Complication | What happens |
|---|---|
Cirrhosis | Permanent liver scarring makes it difficult for the liver to work and may lead to liver failure; occurs in later stages |
Portal hypertension | High blood pressure in the portal vein can cause pressure on digestive-system blood vessels, life-threatening internal bleeding, and enlargement of the liver and spleen |
Liver cancer | PBC increases the risk, particularly in people with cirrhosis |
Osteoporosis | Thinning, weakened, brittle bones that break easily |
Vitamin deficiencies | Bile helps the intestines absorb vitamins A, D, E, and K; reduced bile flow can cause deficiency |
High cholesterol | Up to 80% of people with PBC have high cholesterol |
How PBC Is Diagnosed
Your health care professional performs a physical exam and asks about your health history. Three tests are the primary means of making a diagnosis.
Liver function blood tests check levels of certain proteins in the blood and give information about how well your liver is working. Certain results show a reduction in the transport of bile from the liver.
Antibody tests are the signature test for PBC. Most people with PBC have a positive test for immune system antibodies targeting cells of the lining of the bile ducts — called an antimitochondrial antibody (AMA) test.
Liver biopsy uses a needle to remove a piece of liver that can be studied in a lab. Microscopic exam shows the condition of the bile ducts and liver tissues. The test is usually used only if PBC is suspected but antibody tests are negative.
Diagnostic test | What it does |
|---|---|
Liver function blood tests | Detect reduced bile transport from the liver |
Antimitochondrial antibody (AMA) test | Positive in most people with PBC |
Liver biopsy | Confirms duct and tissue damage; used when antibody tests are negative |
Ultrasound | Rules out other liver diseases such as tumors or bile duct blockages |
MRI / MRCP | Images of the liver, bile ducts, gallbladder, and pancreas to rule out similar conditions |
Elastography (ultrasound or MRE) | Measures liver stiffness to indicate the degree of cirrhosis; monitors progression |
Cholesterol blood test | Cholesterol is often high in people with PBC |
Imaging tests are usually not necessary to make a diagnosis, but they may be used to rule out other diseases or understand the condition of the liver.
Treatment: Slowing the Disease
Medicines may slow the progression of PBC and prevent complications.
Ursodiol (ursodeoxycholic acid) is the first line of treatment for PBC. It is a naturally occurring bile acid that seems less likely to damage bile ducts than some other bile acids. By taking the place of more harmful bile acids, ursodiol may improve liver function tests, delay liver tissue damage, and reduce itching.
Fenofibrate, approved for lowering cholesterol and triglycerides, appears to have some benefit for improving liver function in people with PBC and may reduce itching and extreme tiredness.
PPAR agonists, including elafibranor and seladelpar lysine, affect mechanisms that regulate triglycerides and sugars in the body. They are approved for treatment of PBC and can be taken with ursodiol; they may improve liver function.
A liver transplant is the only treatment known to cure PBC. During a liver transplant, surgeons remove a diseased liver and replace it with a healthy liver from a donor. A transplant is reserved for people with liver failure or other severe complications of PBC — and the disease may appear again after a liver transplant.
Treatment: Controlling the Symptoms
For itching, antihistamines may help reduce mild itching and can cause drowsiness, which may help people kept awake by itchiness. Bile acid sequestrants (such as cholestyramine and colestipol) bind to bile acids — the substances thought to cause itching in liver disease — and treat moderate to severe itching, but they often cause constipation, cannot be used with several other medicines, and may cause a vitamin K deficiency. Rifampin, an antibiotic, may reduce moderate to severe itching when sequestrants cannot be used, but requires regular blood tests because it can cause liver inflammation. Naltrexone, an opioid antagonist typically used for alcohol and opioid use disorders, may reduce moderate to severe itching but cannot be used if there is advanced liver disease.
Itching treatment | Used for | Key considerations |
|---|---|---|
Antihistamines | Mild itching | Drowsiness can help those kept awake by itching |
Bile acid sequestrants (cholestyramine, colestipol) | Moderate to severe itching | Often cause constipation; drug interactions; may cause vitamin K deficiency |
Rifampin | Moderate to severe itching | Requires regular blood tests; can cause liver inflammation |
Naltrexone | Moderate to severe itching | Cannot be used with advanced liver disease |
For dry eyes and mouth, artificial tears and saliva substitutes can help, available with or without a prescription. You can make more saliva and relieve dry mouth by chewing sugarless gum, sucking on sugarless hard candy, or eating dried fruit slices.
Treatment: Managing Complications
Your health care professional may recommend vitamin and mineral supplements — vitamins A, D, E, and K, plus calcium, folic acid, or iron — if your body is not absorbing nutrients. Statins can treat high cholesterol. For weak or thinning bones, calcium and vitamin D supplements reduce bone loss, and exercise such as walking and using light weights most days of the week can help increase bone density.
For portal hypertension with more-advanced scarring, your provider is likely to screen and monitor you for portal hypertension and enlarged veins. If fluid accumulates in the abdominal cavity, mild fluid accumulation can be managed by limiting salt in your diet; more severe cases may require diuretics or a procedure to drain the fluid.

Lifestyle and Home Remedies
Taking good care of your overall health can ease some PBC symptoms and help prevent certain complications. Choose low-sodium foods, since sodium contributes to tissue swelling and the buildup of fluids. Avoid raw or undercooked food — raw or undercooked seafood and meats and unpasteurized dairy products can carry bacteria, and bacterial infections can be dangerous for people with liver disease. Exercise most days of the week to help reduce the risk of bone loss. Avoid alcohol: your liver processes the alcohol you drink, and the added stress can cause liver damage; people with PBC generally should not drink alcohol. And check with your health care professional about any new medicines or dietary supplements, because a liver that is not working well makes you more sensitive to their effects.
Lifestyle step | Why it matters in PBC |
|---|---|
Low-sodium diet | Reduces tissue swelling and fluid buildup |
Avoid raw or undercooked foods | Bacterial infections can be dangerous with liver disease |
Exercise most days | Helps reduce the risk of bone loss |
Avoid alcohol | Extra processing stress can cause further liver damage |
Vet all new medicines and supplements | Impaired liver increases sensitivity to drugs and supplements |
Coping and Support
Living with a long-term liver disease with no cure can be frustrating, and fatigue alone can have a profound impact on quality of life. Learning about your condition helps you take a more active role in your own care — reputable patient organizations such as the American Liver Foundation are a good starting point alongside conversations with your health care professional. Taking time for yourself through eating well, exercising, and getting enough rest helps, and planning ahead for periods when you may need more rest matters. If friends or family offer help with groceries, laundry, or cooking, accept it — PBC can be exhausting. And if loved ones have a hard time understanding your illness, a support group can help.
Preparing for Your Appointment
If you are diagnosed with primary biliary cholangitis, you may be referred to a gastroenterologist (a specialist in diseases of the digestive system) or a hepatologist (a specialist in liver diseases).
Before your visit, be aware of any pre-appointment restrictions, write down your symptoms including anything seemingly unrelated, note key personal information such as major stresses or recent life changes, and make a list of all medicines, vitamins, and supplements you take with doses. Ask a family member or friend to come along — someone else may remember details you miss. And write down questions to ask.
What kinds of tests do I need, and do they require special preparation?
How severe is the damage to my liver?
How will we monitor the health of my liver?
What treatments do you recommend for me?
How will we know if I need a liver transplant?
What side effects can I expect from treatment?
Are there other treatment options?
What changes should I make to my diet?
Expect your doctor to ask about your symptoms, when they began, whether they come and go, what makes them better or worse, family history of liver disease, your history of hepatitis or other liver disease, alcohol use, and all medicines and herbal or natural remedies you take.
Conclusion
Primary biliary cholangitis is a slow, often silent autoimmune disease that attacks the liver's bile ducts — most often in middle-aged and older women, with more than half of people symptom-free at diagnosis. Its hallmark early signals are severe persistent itching and extreme fatigue that rest does not relieve, and its defining diagnostic marker is the antimitochondrial antibody (AMA). Treatment today can slow progression with ursodiol and newer PPAR agonists, control itching and dryness, and manage the cholesterol, bone, and vitamin complications that come with reduced bile flow. A liver transplant remains the only known cure, reserved for liver failure or severe complications.
If you have severe, persistent itching with no obvious cause or unrelenting fatigue, bring it up with your health care professional — a simple blood test can start the conversation. For related reading, see our guide on Portal Hypertension, a complication that can develop as liver damage progresses.
Frequently Asked Questions
What is primary biliary cholangitis?
PBC is an uncommon, long-term (chronic) autoimmune liver disease in which the body's immune system mistakenly attacks the lining of the small- and medium-sized bile ducts within the liver. Bile gradually builds up, damaging and destroying liver tissues. It was formerly called primary biliary cirrhosis.
Who gets primary biliary cholangitis?
PBC most often affects middle-aged and older women. Other risk factors include having a family member with the condition and living in North America or Northern Europe, where it is most common.
What are the symptoms of PBC?
More than 50% of people have no symptoms at diagnosis. When symptoms appear, they most often include fatigue, itchy skin, dry eyes and mouth, and difficulty with memory and concentration. As liver damage worsens, upper right belly pain, xanthomas around the eyes or joints, jaundice, skin darkening, and oily or greasy stools can develop.
How is PBC diagnosed?
Diagnosis relies mainly on blood tests: liver function tests showing reduced bile transport and the antimitochondrial antibody (AMA) test, which is positive in most people with PBC. A liver biopsy is usually reserved for cases where PBC is suspected but antibody tests are negative. Imaging tests are used to rule out other conditions.
Is there a cure for primary biliary cholangitis?
A liver transplant is the only treatment known to cure PBC. It is reserved for people with liver failure or other severe complications, and the disease may appear again after a transplant.
What is the first-line treatment for PBC?
Ursodiol (ursodeoxycholic acid), a naturally occurring bile acid that takes the place of more harmful bile acids. It may improve liver function tests, delay liver tissue damage, and reduce itching. Newer approved options include fenofibrate and PPAR agonists (elafibranor, seladelpar), which can be taken with ursodiol.
Why do people with PBC get itchy?
The bile acids thought to cause itching in liver disease build up as bile flow decreases. Treatments range from antihistamines for mild itching to bile acid sequestrants, rifampin, or naltrexone for moderate to severe itching.
Can PBC cause high cholesterol and weak bones?
Yes. Up to 80% of people with PBC have high cholesterol, and impaired bile flow reduces absorption of the fat-soluble vitamins A, D, E, and K, contributing to thinning bones (osteoporosis). Statins, vitamin and mineral supplements, calcium, vitamin D, and regular exercise are used to manage these complications.
Further Reading
Medical disclaimer: This article is for general informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of a qualified health care provider with any questions you may have regarding a liver condition or other health concern. Never disregard professional medical advice or delay seeking it because of content you have read on this site.
Comments