Tetralogy of Fallot: A Parent's Guide to the Heart Condition Babies Are Born With — Symptoms, Diagnosis, and Surgery

Updated: 2 days ago
Medically reviewed by Dr. Baraa Alnahhal, MD · Last reviewed: September 2026
Tetralogy of Fallot: A Parent's Guide to the Heart Condition Babies Are Born With — Symptoms, Diagnosis, and Surgery
Source currency note: this guide reflects medical information reviewed in May 2026. Always confirm current guidance with your healthcare professional.
TL;DR
Tetralogy of Fallot (pronounced teh-TRAL-uh-jee of fuh-LOW) is a rare congenital heart defect — meaning it is present at birth. It combines four structural changes in the heart: a narrowed valve to the lungs, a hole between the lower chambers, the aorta in the wrong place, and a thickened right heart chamber. Babies often have blue or gray skin from low oxygen. The key point: every baby with this condition needs surgery, usually in the first year of life, followed by regular heart checkups for life. Long-term survival keeps improving.
Quick Answer
What is tetralogy of Fallot? A rare heart defect present at birth that combines four structural changes in the heart and alters blood flow through the body.
What does it look like? Babies often have blue or gray skin, breathe fast, tire easily, struggle to gain weight, and may cry for long periods.
What are tet spells? Sudden episodes of deep blue or gray skin, nails, and lips, most common around 2 to 4 months old. Place the baby on the side with knees pulled to the chest and call 911.
How is it treated? Every baby needs surgery — a temporary shunt and/or open-heart repair, usually in the first year of life.
What's the outlook? Long-term survival keeps improving, but lifelong checkups with a heart specialist team are essential.
What is tetralogy of Fallot?
Tetralogy of Fallot is a heart condition that develops while the baby's heart grows during pregnancy. It is a type of congenital heart defect, and it is rare.
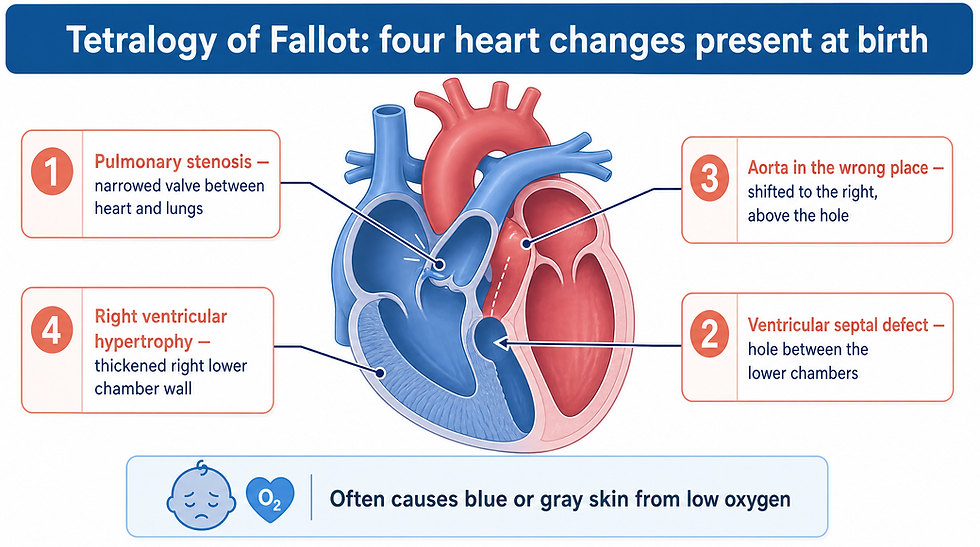
Despite the complicated name, the condition is really a combination of four specific heart changes that occur together. Because of these changes, blood does not flow normally through the heart and out to the rest of the body.
Babies with tetralogy of Fallot often have blue or gray skin color because their blood carries less oxygen than it should. In most cases, the condition is found during pregnancy or soon after birth. If the heart changes and symptoms are mild, it may not be noticed or diagnosed until adulthood.
Every baby with tetralogy of Fallot needs surgery to fix the heart, and every child with it needs regular health checkups for life.
The four heart changes in tetralogy of Fallot
Each of the four changes affects the heart's structure and how blood moves through it. Here is what each one means in plain language.
| Heart change | What it means | | --- | --- | | Pulmonary valve stenosis | The valve between the heart and the lungs is narrowed, so less blood reaches the lungs. In some cases the valve never forms and a solid sheet of tissue blocks blood flow — called pulmonary atresia. | | Ventricular septal defect (VSD) | A hole between the bottom chambers of the heart. Oxygen-poor blood mixes with oxygen-rich blood, and the heart has to work harder, which may weaken it over time. | | Aorta in the wrong place | The aorta — the body's main artery — is shifted to the right and sits directly above the hole in the heart wall, changing how blood flows to the lungs. | | Right ventricular hypertrophy | Because the heart works too hard, the wall of the right lower chamber thickens. Over time, this can make the heart weaker. |
Some people with tetralogy of Fallot have other changes too, such as differences in the aorta or heart arteries, or a hole between the upper chambers called an atrial septal defect.
Tetralogy of Fallot symptoms
Symptoms depend on how much blood flow is blocked from leaving the heart to reach the lungs. The more blocked the flow, the more noticeable the symptoms.
Common symptoms include blue or gray skin color — which may be harder or easier to see depending on a baby's skin tone — plus shortness of breath and rapid breathing, especially during feeding or exercise. Babies may also have trouble gaining weight, get tired easily during play, become unusually cranky, cry for long periods, or faint.
What are tet spells?
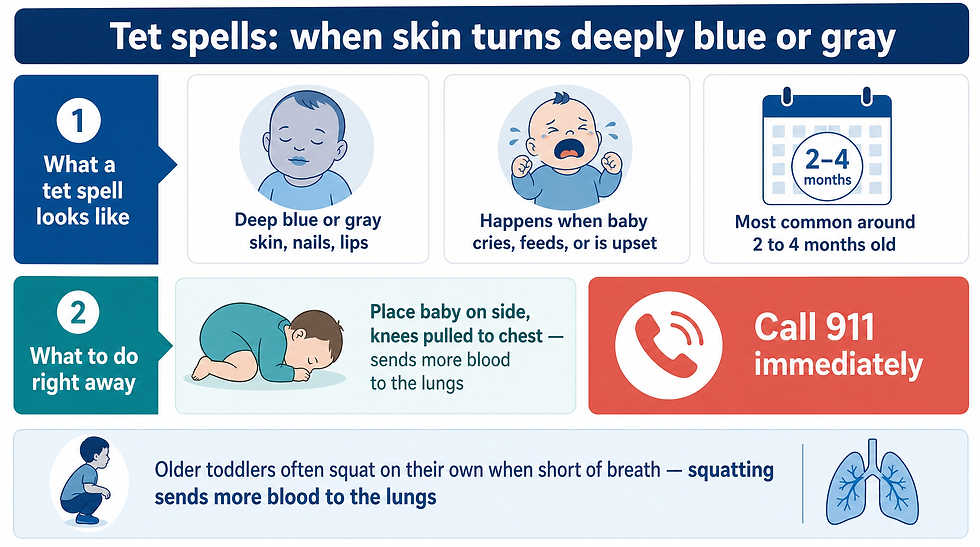
Some babies with tetralogy of Fallot suddenly develop deep blue or gray skin, nails, and lips. These episodes are called tet spells. They usually happen when the baby cries, eats, or is upset.
Tet spells are caused by a rapid drop in the amount of oxygen in the blood. They are most common in young infants around 2 to 4 months old. In toddlers and older children, tet spells may be harder to notice — but these children often squat when short of breath, because squatting sends more blood to the lungs.
Tetralogy of Fallot risk factors
The exact cause of tetralogy of Fallot is not known. It happens during pregnancy, when the baby's heart grows. However, some things may raise the risk of a baby being born with it.
| Risk factor | Detail | | --- | --- | | Family history | A family history of the condition raises the risk. | | Viral infection during pregnancy | Including rubella (German measles). | | Alcohol during pregnancy | Drinking alcohol during pregnancy may raise the risk. | | Poor diet during pregnancy | Eating poorly during pregnancy is a listed risk factor. | | Smoking during pregnancy | Smoking during pregnancy may raise the risk. | | Maternal age | Being older than 35 during pregnancy. | | Certain conditions in the baby | Down syndrome or DiGeorge syndrome. |
When to see a doctor — and emergency action for a tet spell
Serious congenital heart conditions such as tetralogy of Fallot are often diagnosed before or soon after a baby is born. Seek medical help if you notice that your baby has trouble breathing, blue or gray skin, lack of alertness, seizures, weakness, or is more cranky than usual.
If your baby's skin becomes blue or gray: Place your baby on the side and pull the baby's knees up to the chest. This helps increase blood flow to the lungs. Call 911 or your local emergency number right away.
How is tetralogy of Fallot diagnosed?
Tetralogy of Fallot is often diagnosed soon after birth. The baby's skin may look blue or gray, and a whooshing sound — called a heart murmur — may be heard when a doctor listens with a stethoscope.
Several tests confirm the diagnosis and help plan treatment.
| Test | What it does | | --- | --- | | Pulse oximetry | A small sensor on a finger or toe quickly checks the amount of oxygen in the blood. | | Echocardiogram | Sound waves create moving pictures of the heart, showing the heart and valves and how well they are working. | | Electrocardiogram (ECG or EKG) | Sticky electrode patches on the chest, arms, or legs measure how the heart is beating. It can detect irregular heartbeats and signs of an enlarged heart. | | Chest X-ray | Shows the shape and condition of the heart and lungs. A classic sign of tetralogy of Fallot is a boot-shaped heart, which means the right lower chamber is too big. | | Cardiac catheterization | Thin, flexible tubes called catheters are guided to the heart through a blood vessel, usually in the groin. It helps diagnose or treat some heart conditions and is often used to plan surgery. |
Treatment: every baby needs surgery
All babies with tetralogy of Fallot need treatment with surgery to fix the heart and improve blood flow. A cardiovascular surgeon performs the operation, and the timing and type of surgery depend on the baby's overall health and the specific heart changes. Some babies receive medicine while waiting for surgery to keep blood flowing from the heart to the lungs.
| Surgery type | What happens | When it is used | | --- | --- | --- | | Temporary repair (palliative shunt) | A surgeon places a tube called a shunt between a large artery off the aorta and the lung artery, creating a new path for blood to reach the lungs. The shunt is removed during the open-heart surgery. | If a baby is born early or the lung arteries are not fully developed. | | Complete repair (open-heart surgery) | The surgeon patches the hole between the lower chambers, repairs or replaces the pulmonary valve, and may remove thickened muscle below the valve or widen the smaller lung arteries. | Usually done in the first year of life. Even adults who were never treated in childhood may still benefit from surgery. |
After a complete repair, the right lower chamber does not need to work as hard. Its wall should return to its usual thickness, the oxygen level in the blood rises, and symptoms usually improve.

Outlook and lifelong care
The long-term survival rates for people who have had tetralogy of Fallot surgery continue to improve. Still, people with the condition need lifelong care, ideally from a healthcare team that specializes in heart diseases. Checkups often include imaging tests to see how well the heart is working and to check for surgery complications.
Possible complications after surgery include backward flow of blood through a heart valve, irregular heartbeats, a hole that does not go away after surgery, changes in the size of the heart chambers, swelling of part of the aorta (aortic root dilation), and sudden cardiac death. Another treatment or surgery may sometimes be needed to fix these.
Without treatment, tetralogy of Fallot usually leads to life-threatening complications that may cause disability or death by early adulthood. A further risk is infective endocarditis — infection of the inner lining of the heart or heart valves — which is why doctors sometimes recommend antibiotics before dental work for people with the condition.
Preparing for your appointment
Serious congenital heart defects like tetralogy of Fallot are typically diagnosed during pregnancy or soon after birth. If you think your child has a heart condition that was not noticed at birth, talk with the healthcare team and be prepared to describe your child's symptoms. It also helps to ask family members whether anyone was born with a heart defect, since some congenital heart defects occur in families.
Before the visit, make a list of your baby's symptoms — including any that do not seem related — and write down your family history from both sides of the family. Note any medicines, vitamins, or supplements taken during pregnancy. Bring a family member or friend if possible, since it can be hard to remember everything discussed during an appointment. Write down questions in advance.
Useful questions to ask include: What is the most likely cause? What tests are needed, and do they require preparation? What treatments are available and which do you recommend? What are the possible complications of treatment? What is the outlook after surgery? Are there activity restrictions, and can my child play sports or attend gym class?
Expect the doctor to ask when you first noticed symptoms, how often they occur, whether anything makes them better, whether there is a family history of congenital heart defects, and whether your child is growing and meeting developmental milestones as expected.
Prevention: lowering the risk of heart defects
Because the exact cause of most congenital heart defects is not known, it may not be possible to prevent them. If you are at higher risk of having a child with a congenital heart defect, genetic testing and screening may be done during pregnancy.
There are several steps that may help lower the overall risk of birth defects. Getting proper prenatal care with regular checkups keeps both parent and baby healthy. Taking a multivitamin with 400 micrograms of folic acid daily lowers the risk of birth defects in the brain and spinal cord, and may help lower heart defect risk as well. Avoiding alcohol and smoking — including secondhand smoke — matters, and getting the rubella vaccine before trying to get pregnant can protect a baby's heart development. Managing blood sugar if you have diabetes, managing long-term conditions such as phenylketonuria, staying away from strong-smelling paints and cleaning products during pregnancy, and checking with your healthcare team before taking any medicines during pregnancy all help too.
Living well after treatment
After treatment, your healthcare team may suggest steps to keep the heart healthy. Some people born with a serious heart condition may need to limit certain sports or exercise, but many others can take part in such activities — so always ask your healthcare team which sports are safe.
Good oral care and regular dental checkups help prevent heart infection (endocarditis). Antibiotics may also be recommended before dental treatments, especially for people who have a mechanical heart valve.
Living with a congenital heart condition can be stressful for the whole family. Talking with a support group, a therapist, or a counselor can help you and your child manage stress and anxiety, and your care team can suggest resources in your area.
Conclusion and next steps
Tetralogy of Fallot is a serious but treatable heart defect. The most important facts for any family: every baby with this condition needs surgery, usually in the first year of life, and lifelong follow-up with a heart specialist team is essential for lasting health.
If your newborn has blue or gray skin, rapid breathing, poor feeding, or unusual crankiness, talk with your pediatrician promptly — these can be early signs of a heart condition. If your baby ever has a tet spell, place them on the side with knees pulled to the chest and call 911 right away. For families managing this diagnosis, come to appointments prepared with a symptom list, family history, and written questions, and ask specifically about safe activity levels and dental antibiotic guidance as your child grows.
FAQ
Is tetralogy of Fallot curable?
Surgery — usually a complete repair in the first year of life — fixes the structural problems for most babies. Oxygen levels rise and symptoms usually improve, but lifelong heart checkups remain necessary because heart valve leakage or rhythm problems can develop later.
Can a baby with tetralogy of Fallot live a normal life?
Many children attend school and live active lives after repair, and long-term survival keeps improving. However, some may need limits on certain sports, occasional additional procedures, and regular specialist monitoring.
What causes tetralogy of Fallot?
The exact cause is not known. It develops during pregnancy as the baby's heart forms. Family history, a rubella infection during pregnancy, alcohol or smoking during pregnancy, maternal age over 35, and conditions such as Down syndrome or DiGeorge syndrome can raise the risk.
Why do babies with tetralogy of Fallot turn blue?
The four heart changes let oxygen-poor blood flow out to the body instead of going to the lungs. With less oxygen in the blood, the skin, nails, and lips can look blue or gray.
What should I do during a tet spell?
Place the baby on the side and pull the knees up to the chest — this position sends more blood to the lungs. Then call 911 or your local emergency number immediately.
Does tetralogy of Fallot run in families?
It can. A family history of the condition raises the risk, so ask relatives on both sides of the family whether anyone was born with a congenital heart defect and share that information with the healthcare team.
References
Tetralogy of Fallot — Symptoms & Causes. https://www.mayoclinic.org/diseases-conditions/tetralogy-of-fallot/symptoms-causes/syc-20353477
Tetralogy of Fallot — Diagnosis & Treatment. https://www.mayoclinic.org/diseases-conditions/tetralogy-of-fallot/diagnosis-treatment/drc-20353482
This article is for general information only and is not a substitute for professional medical advice. Always consult a qualified healthcare provider for diagnosis and treatment.
Comments