Microscopic Polyangiitis (MPA): Understanding Rare Blood Vessel Inflammation

Updated: Nov 11
Medically reviewed by Dr. Baraa Alnahhal, MD · Last reviewed: October 2026
Quick Answer
Microscopic polyangiitis (MPA) is a rare form of vasculitis that causes inflammation in small blood vessels throughout the body, most often affecting the kidneys and lungs. It can lead to kidney failure or lung scarring. Diagnosis involves blood tests, imaging and biopsies. Immunosuppressive medications control inflammation, and most people reach remission, though long-term monitoring is needed.
What the research says
Rituximab works as well as cyclophosphamide for inducing remission. In 197 patients with granulomatosis with polyangiitis or microscopic polyangiitis, 64% on rituximab versus 53% on cyclophosphamide reached remission off prednisone at 6 months; in relapsing disease the figures were 67% versus 42%. (Stone et al., N Engl J Med, 2010) [3]
Long-term kidney and survival outcomes are similar with either drug. In 595 real-world patients (70% MPO-ANCA positive), the 5-year risk of kidney failure or death did not differ between rituximab- and cyclophosphamide-based induction (hazard ratio 1.03). (Wallace et al., Arthritis Rheumatol, 2023) [4]
What Is Microscopic Polyangiitis?
Microscopic polyangiitis (MPA) is a rare and complex autoimmune condition classified as a type of vasculitis. The name itself provides insight into the nature of the disease: "microscopic" refers to its impact on small blood vessels, "poly" indicates it can affect many areas of the body, and "angiitis" is a synonym for vasculitis or blood vessel inflammation. When these small vessels become inflamed, their walls may thicken and narrow, restricting vital blood flow to organs. Alternatively, the vessel walls can become thin and weak, leading to bleeding in surrounding tissues. Both forms of damage can result in significant organ dysfunction, particularly in the kidneys, lungs, nerves, skin, and joints.
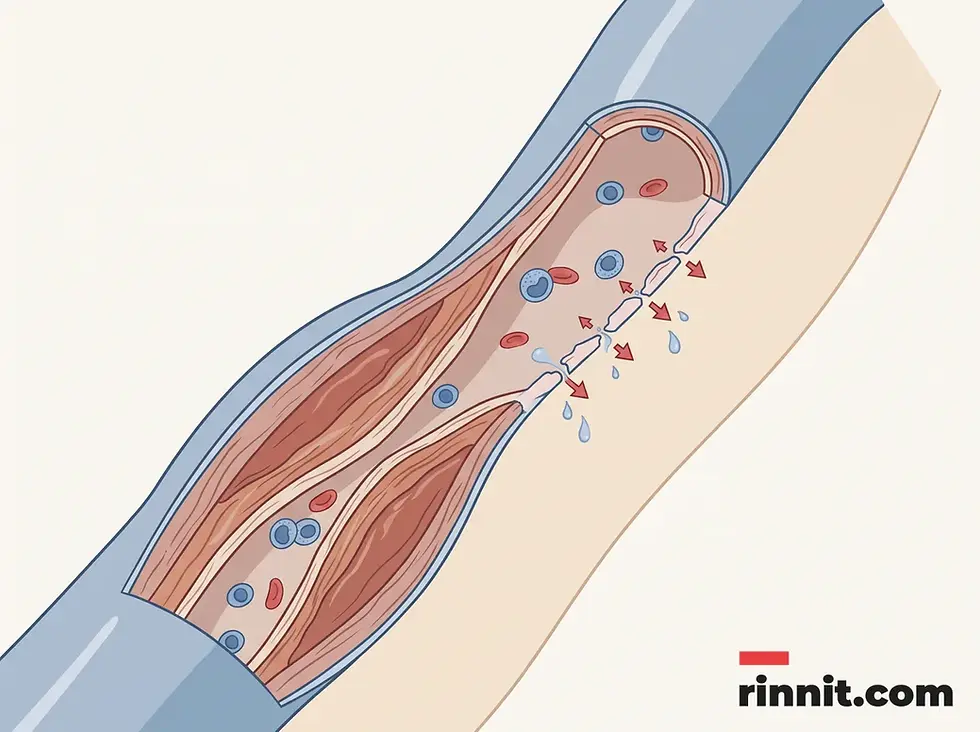
As an autoimmune disorder, MPA occurs when the body's immune system mistakenly attacks its own healthy tissues rather than protecting them from external invaders. While the precise trigger for this response remains a subject of ongoing research, many healthcare providers associate the condition with antineutrophil cytoplasmic antibodies (ANCA). These autoantibodies are present in approximately 70% of individuals at the time of their diagnosis. MPA can affect anyone, though it is slightly more prevalent in males and is most commonly diagnosed in individuals around the age of 50.
What are the symptoms of microscopic polyangiitis (MPA), and which organs does it affect?
The symptoms of microscopic polyangiitis are diverse, reflecting the wide range of organs the disease can affect. While general signs of illness like fatigue and fever are common, more specific symptoms arise depending on which small blood vessels are most heavily impacted by inflammation.
Kidneys: blood in urine, cloudy urine, or no visible symptoms. The potential complication is kidney failure.
Lungs: shortness of breath, a persistent cough, or coughing up blood. Potential complications include lung scarring (pulmonary fibrosis) and bleeding.
Skin: rashes, particularly on the legs, which can reflect tissue damage or localized inflammation.
Nerves: tingling, numbness, or muscle weakness, with a risk of permanent nerve damage.
Joints and muscles: joint pain and muscle aches, which can lead to chronic discomfort and mobility issues.
General: fatigue, fever, loss of appetite, and unexplained weight loss, which can signal an overall decline in health and well-being.
It is important to note that kidney involvement is nearly universal in MPA cases, yet it often proceeds without noticeable symptoms until significant damage has occurred. Regular monitoring of urine and blood health is therefore a critical component of early detection and ongoing management.

How is microscopic polyangiitis (MPA) diagnosed?
Diagnosing microscopic polyangiitis requires a comprehensive evaluation of a patient's health history and current symptoms. Because MPA shares symptoms with many other conditions, healthcare providers often employ a "differential diagnosis" approach, ruling out more common illnesses before confirming a rare vasculitis. The process typically begins with a physical examination, followed by blood and urine tests to check for inflammation markers and kidney function. A chest X-ray is often used to assess lung health.
If MPA is suspected, more specialized imaging such as CT scans or MRIs may be ordered to visualize organ damage. In many cases, a biopsy (the removal of a small tissue sample from an affected organ like the kidney or lung) is necessary to confirm the presence of blood vessel inflammation. Patients usually work with a multidisciplinary team, including a rheumatologist specializing in inflammatory diseases and, if the kidneys are affected, a nephrologist or kidney specialist.
How is microscopic polyangiitis (MPA) treated and managed long term?
The primary goal of treating microscopic polyangiitis is to control inflammation and prevent further damage to blood vessels and organs. Achieving "remission", a state where there is no active inflammation, is the central focus of the medical team. Treatment typically involves a combination of medications:
Glucocorticoids: Medications like prednisone are used to rapidly reduce inflammation, often starting at higher doses before being gradually tapered down.
Immunosuppressants: These drugs help regulate the immune system's overactive response. They are often required for long-term management, sometimes for the remainder of a patient's life, to maintain remission and prevent relapses.
Monitoring is a lifelong commitment for those with MPA. Regular follow-up appointments, blood tests, and screenings are necessary to ensure the treatment remains effective and to catch any signs of a relapse early. A relapse occurs when symptoms return after a period of remission; while some patients may never experience one, others may go months or years between active flares of the disease.

Conclusion
While microscopic polyangiitis is a serious and life-altering diagnosis, it is a treatable condition. The advancement of immunosuppressive therapies has made it possible for the majority of patients to achieve and maintain remission, significantly improving their long-term outlook. By working closely with a specialized healthcare team and staying vigilant for new or worsening symptoms, individuals with MPA can successfully manage the disease and protect their vital organ functions.
When should you seek care for microscopic polyangiitis (MPA)?
If you are experiencing unexplained fatigue, persistent joint pain, or changes in your respiratory health, consult a healthcare provider for a thorough evaluation. For those already diagnosed with MPA, prioritize your scheduled follow-up appointments and laboratory tests. Early intervention and consistent adherence to your treatment plan are the most effective ways to ensure long-term health and prevent serious complications.
Frequently Asked Questions
What is microscopic polyangiitis (MPA)?
Microscopic polyangiitis (MPA) is a rare autoimmune disease that causes inflammation in small blood vessels throughout the body.
Which organs does MPA affect most?
MPA most commonly affects the kidneys, lungs, nerves, skin, and joints.
Is MPA a type of cancer?
No, it is an autoimmune disease and a form of vasculitis, not cancer.
What are the most common symptoms?
Fatigue, fever, weight loss, skin rashes, shortness of breath, and joint pain are common signs.
Does MPA always affect the kidneys?
Yes, it almost always involves the kidneys, though you may not feel any symptoms initially.
What are ANCA antibodies?
ANCA antibodies are autoantibodies that target healthy tissue and are found in about 70% of MPA patients.
How is MPA diagnosed?
Diagnosis involves blood and urine tests, imaging (X-rays, CT, MRI), and often a tissue biopsy.
Can MPA be cured?
There is no cure, but the disease can be managed effectively to achieve long-term remission.
What is remission in MPA?
Remission is a state where there is no active inflammation damaging your blood vessels or organs.
What medications are used for treatment?
Healthcare providers typically prescribe glucocorticoids (like prednisone) and immunosuppressants.
How long does treatment last?
Treatment varies, but many people need to take immunosuppressants for a long time, sometimes for life.
What is a relapse?
A relapse is when symptoms return after a period of remission.
Is MPA more common in men or women?
MPA is slightly more common in males.
At what age does MPA usually develop?
MPA most commonly develops in people around the age of 50.
What are the risks of untreated MPA?
Untreated MPA can lead to life-threatening complications like kidney failure or lung bleeding.
Medical disclaimer: The information provided in this article is for educational purposes only and is not intended as a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition.
Source date: December 9, 2025. This article is current based on the most recent available data from the primary source.
Related Reading
ANCA Test: c-ANCA vs p-ANCA, What It Checks and What Results Mean explains the blood test for antibodies linked to small-vessel vasculitis.
References
Mayo Clinic Staff. Granulomatosis with polyangiitis - Symptoms and causes. Mayo Clinic. January 14, 2025. https://www.mayoclinic.org/diseases-conditions/granulomatosis-with-polyangiitis/symptoms-causes/syc-20351088
Mayo Clinic Staff. Granulomatosis with polyangiitis - Diagnosis and treatment. Mayo Clinic. January 14, 2025. https://www.mayoclinic.org/diseases-conditions/granulomatosis-with-polyangiitis/diagnosis-treatment/drc-20351093
Stone JH, et al. Rituximab versus cyclophosphamide for ANCA-associated vasculitis. New England Journal of Medicine. 2010;363(3):221-232. PMID 20647199. https://doi.org/10.1056/NEJMoa0909905
Wallace ZS, et al. Comparative effectiveness of rituximab- versus cyclophosphamide-based remission induction strategies in antineutrophil cytoplasmic antibody-associated vasculitis for the risk of kidney failure and mortality. Arthritis & Rheumatology. 2023;75(9):1599-1607. PMID 37011036. https://doi.org/10.1002/art.42515



Comments