AA Amyloidosis: What It Is, Why Inflammation Triggers It, and How Treatment Works

Updated: Nov 11
Medically reviewed by Dr. Baraa Alnahhal, MD · Last reviewed: October 2026
This article is for general education only and is not a substitute for professional medical advice, diagnosis, or treatment. Always consult a qualified healthcare provider about your own health. Content is based on medically reviewed clinical sources last updated June 23, 2022, and current peer-reviewed literature.
Quick Answer: What Is AA Amyloidosis and How Is It Treated?
AA amyloidosis is a protein misfolding disorder in which serum amyloid A forms rigid fibrils that build up in organs, primarily the kidneys. It complicates chronic inflammatory conditions such as rheumatoid arthritis and inflammatory bowel disease. Diagnosis requires a biopsy with Congo red staining, and treatment controls the underlying inflammation to lower SAA levels, ideally below 10 mg/L.

What the research says
Keeping inflammation low is the key to survival. Following 374 people with AA amyloidosis for a median of about 7 years, median survival was 133 months. Those with the highest levels of the inflammation protein SAA had a 17.7 times higher risk of death than those with the lowest, and amyloid deposits shrank in 60% of people whose SAA stayed below 10 mg per liter (Lachmann et al., NEJM, 2007).
A drug that blocks amyloid build-up slowed kidney decline. In 183 people with AA amyloidosis affecting the kidneys, eprodisate lowered the risk of worsening kidney function or death over 2 years (hazard ratio 0.58) and slowed the yearly fall in kidney filtration (10.9 vs 15.6 ml/min), but did not change the need for dialysis or death rates (Dember et al., NEJM, 2007).
What exactly is AA amyloidosis?
Amyloidosis is a group of rare disorders in which abnormal proteins lose their correct three-dimensional structure and become twisted, misshapen clumps called amyloid deposits. These deposits gather on tissues and organs and disrupt how they work. Doctors classify amyloidosis by the protein that misfolds, and AA amyloidosis is the type driven by the protein serum amyloid A (SAA), hence the name [1].
AA amyloidosis is also known as secondary amyloidosis, because it never occurs on its own. It is a complication of another ongoing disease process: long-term inflammation keeps SAA protein levels chronically elevated in the bloodstream, and over time the excess protein misfolds and accumulates [1] [2].
In plain terms: your body produces SAA as a normal emergency response to inflammation. When inflammation never switches off, the emergency protein is produced non-stop, gets stuck in its misfolded form, and gradually clogs up organs.
What causes AA amyloidosis?
AA amyloidosis happens when you have high levels of inflammation in your body over a long period, which boosts serum amyloid A protein levels in your bloodstream. Only a small share of people with chronic inflammatory diseases ever develop it, the deposits form in fewer than 5% of patients with chronic inflammatory disorders, which is why it is classified as a rare disease [1] [3].
SAA is an acute-phase protein made by the liver. Its production is switched on by inflammatory signals such as interleukin-1, interleukin-6, and tumor necrosis factor. During an acute inflammatory event, SAA can surge from a normal level below 5 mg/L to over 2,000 mg/L within 24 to 48 hours. In chronic inflammation, it stays persistently high, and that is the environment in which amyloid fibrils form [2] [4].
Class of underlying disease | Examples | Notes |
Rheumatic / autoimmune diseases | Rheumatoid arthritis, juvenile idiopathic arthritis | Classic triggers in Western countries; AA develops in about 1 to 5% of patients with these conditions |
Chronic bacterial infections | Chronic skin ulcers, osteomyelitis, bronchiectasis, tuberculosis | Still major drivers in some regions; declining in countries with strong antimicrobial access |
Inflammatory bowel diseases | Crohn's disease, ulcerative colitis | Gut inflammation keeps SAA elevated for years |
Inherited periodic fever syndromes | Familial Mediterranean fever (FMF), TRAPS | Lifelong autoinflammatory disease, comparatively higher individual risk |
Blood cancers and others | Certain lymphomas, mesothelioma, Castleman disease | Less common associations |
No identifiable cause | Idiopathic AA amyloidosis | About 25% of cases, the source of inflammation remains unclear |
An important nuance for diagnosis: in nearly 25% of AA cases, no clear source of inflammation is ever found (idiopathic AA amyloidosis), and researchers have proposed that obesity may play a role in some of these cases [3]. And surprisingly, up to 10% of people with AA amyloidosis have no clinically obvious chronic inflammatory disease at all, which is one reason it can be missed or misdiagnosed as the more common AL amyloidosis [4].
Which organs does AA amyloidosis affect?
The kidney is the dominant target. In AA amyloidosis, the kidney is involved in virtually all patients, and renal disease drives the clinical picture. The most frequent presentation is protein leaking into urine (proteinuria), which can progress to nephrotic syndrome and then end-stage kidney failure. More than 90% of patients show proteinuria at presentation, and in one large cohort, kidney function was already reduced at diagnosis, with a median creatinine clearance of 41 mL/min [3] [5].
Beyond the kidneys, amyloid deposits also land on the liver and spleen (causing enlargement), the stomach and intestines (causing diarrhea and occasionally bleeding), and the adrenal glands. Heart involvement occurs but is rare, clinically significant cardiac disease appears in roughly 5% of cases and is usually mild when it does occur [3] [4].
Organ | How often involved | Typical effect |
Kidneys | Nearly 100% (dominant organ) | Proteinuria, nephrotic syndrome, kidney failure |
Liver | Frequent | Enlargement |
Spleen | Frequent | Enlargement |
Stomach and intestines | Common in advanced disease | Chronic diarrhea, occasional bleeding |
Adrenal glands | Recognized site | Often subclinical |
Heart | Rare (~5% clinically significant) | Usually mild |
End-stage kidney failure accounts for the cause of death in an estimated 40 to 60% of AA amyloidosis cases, which makes the kidneys the organ that most determines survival [4].
What are the symptoms of AA amyloidosis?
Because AA amyloidosis typically follows many years of active inflammatory disease, early symptoms are easy to mistake for the underlying illness itself. The first warning signs usually come from the kidneys [3].
Symptoms associated with AA amyloidosis include [1]:
Symptom | What it signals |
Swollen feet and legs | Kidney problems / chronic kidney disease |
Foamy or frothy urine | Protein leaking into urine (proteinuria) |
Peeing less than usual | Declining kidney function |
Chronic diarrhea | Deposits in the stomach and intestines |
Enlarged kidney | Amyloid infiltration of the kidney |
Enlarged liver | Amyloid infiltration of the liver |
Low blood pressure | Autonomic or cardiac effects |
Nausea and vomiting | Kidney dysfunction and uremia |
Two red flags deserve emphasis. Foamy, frothy urine is the classic early sign of proteinuria, it means the kidneys' filtering units are leaking protein and should prompt testing. And in someone with a long history of rheumatoid arthritis, Crohn's disease, recurrent fevers, or chronic infection, new leg swelling plus frothy urine should raise suspicion for AA amyloidosis specifically [1] [3].

How is AA amyloidosis diagnosed?
AA amyloidosis is confirmed with a tissue biopsy rather than a blood test, since no blood test can diagnose AA amyloidosis on its own. The definitive diagnosis requires a tissue biopsy: a small sample of tissue is stained with Congo red dye, and under polarized light microscopy, amyloid deposits glow with a characteristic apple-green birefringence. The biopsy also has to prove the deposits are the AA type (not AL or another form), typically with immunohistochemistry or mass spectrometry typing [1] [2] [3].
In practice, diagnosis often starts with a simple fat pad biopsy, a needle sample of abdominal fat just under the skin, and may be followed by an organ biopsy of the affected tissue (kidney, liver, or other) if the fat pad is negative [1].
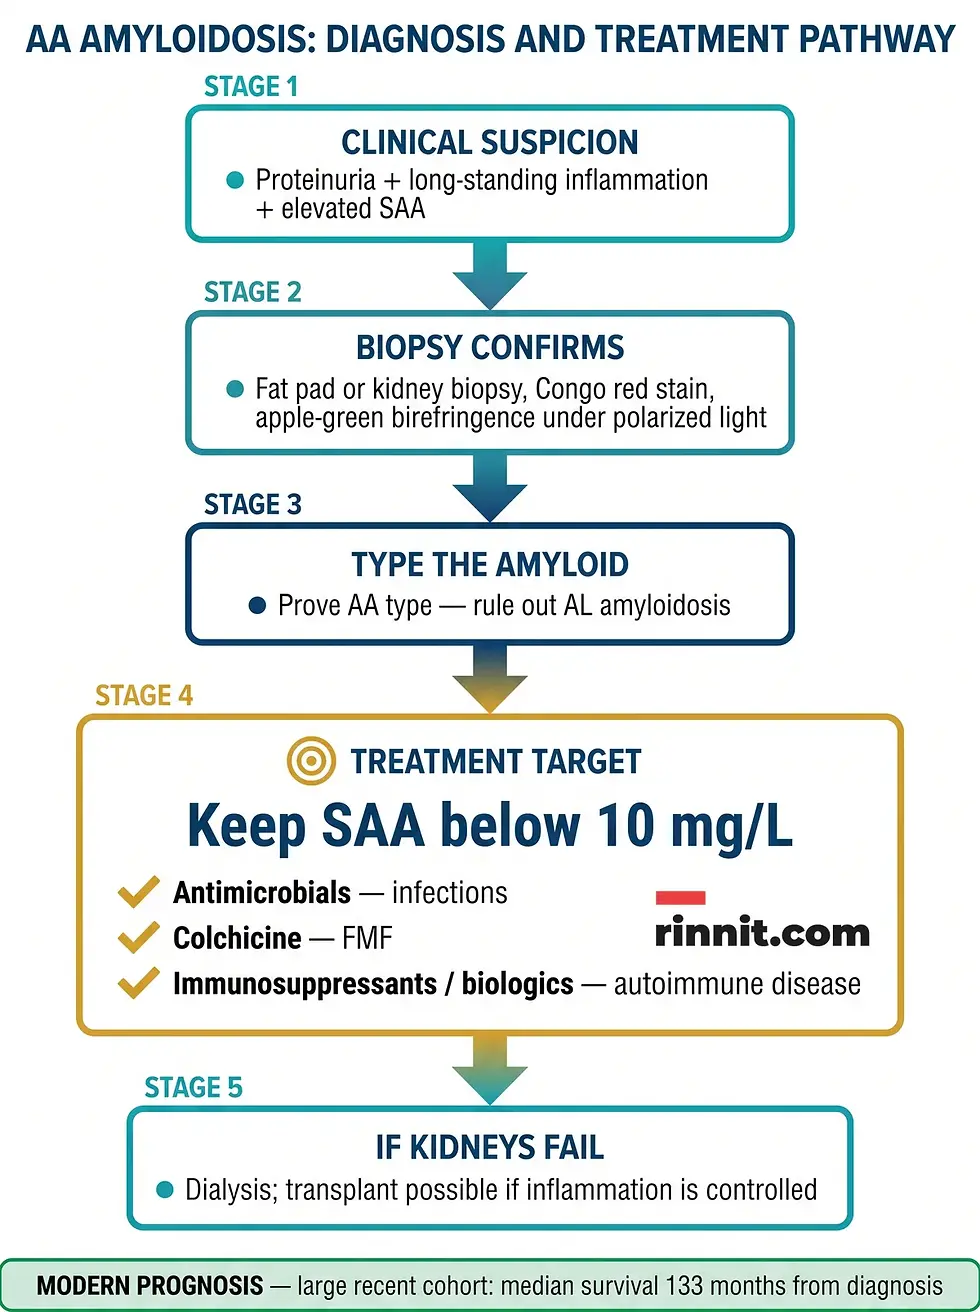
The diagnostic sequence generally follows these steps:
Clinical suspicion: proteinuria or kidney dysfunction in someone with long-standing inflammatory disease, plus persistently elevated SAA levels.
Blood and urine tests: serum creatinine, estimated GFR, 24-hour proteinuria, serum albumin, and SAA concentration.
Fat pad biopsy with Congo red staining.
Organ biopsy if needed (kidney is most informative).
Typing the amyloid to confirm the AA subtype and rule out AL amyloidosis, which looks similar but behaves more aggressively [1] [2] [3].
Ruling out AL amyloidosis matters because the two are treated very differently, AL requires urgent blood-cancer-directed therapy, while AA requires inflammation control [1].
Is AA amyloidosis curable, and how is it treated?
Yes, and this is one of the more hopeful features of AA amyloidosis. Because the disease is caused by chronic inflammation, treating the underlying inflammatory condition treats the amyloidosis itself. When the inflammation is brought under control, SAA production falls, new deposits stop forming, and existing organ dysfunction can stabilize and even improve [1] [3].
The treatment strategy has a clear target: bring the SAA concentration down to an ideal goal of less than 10 mg/L, the level at which the risk of disease progression is minimized and organ recovery becomes possible [3].
Treatment approach | How it works | When it applies |
Treat the underlying cause (foundation) | Removes the driver of chronic SAA overproduction | Every patient, always |
Antimicrobial therapy | Eradicates chronic infections (e.g., chronic ulcers, osteomyelitis) | Infection-driven AA |
Colchicine | Prevents attacks of familial Mediterranean fever, the key inherited trigger | FMF-related AA |
Immunosuppressive agents / biologics | Suppress autoimmune inflammation (e.g., in rheumatoid arthritis, IBD) | Autoimmune-driven AA |
Organ support | Kidney failure managed with dialysis; kidney transplant if underlying disease is controlled | End-stage renal disease |
Emerging therapies (in development) | Agents that clear SAA fibrils from the bloodstream and lab-made antibodies that target deposits already in organs | Clinical research |
One caution about prognosis and treatment: outcomes depend heavily on how early the diagnosis is made and how well the SAA level can be sustained at low concentrations. Poor prognosis factors include older age, low serum albumin, kidney failure already present at diagnosis, and persistently elevated SAA during follow-up. Patients whose AA amyloidosis is rooted in chronic infection historically had worse outcomes, partly because the underlying infections themselves are harder to control [3].
Survival data has improved substantially. Older studies quoted a median survival of roughly two years, but a large modern cohort of 374 AA amyloidosis patients followed a median survival of 133 months (over 11 years) from diagnosis, reflecting better inflammation control in the modern treatment era [11].
How does AA amyloidosis compare to other types?
AA amyloidosis must be told apart from other types of amyloidosis because the wrong treatment for either type is a dangerous mistake, and the same biopsy-and-stain test identifies which type you have.
Feature | AA amyloidosis | AL amyloidosis (most common type in the West) |
Misfolded protein | Serum amyloid A (SAA) | Immunoglobulin light chains |
Root cause | Chronic inflammation | Plasma cell disorder (blood cancer family) |
Dominant organ | Kidneys (~100% involved) | Heart and kidneys |
Rarity | Develops in <5% of chronic inflammation patients | About 12 per million per year in the U.S. |
Treatment target | Control underlying inflammation (SAA <10 mg/L) | Chemotherapy / stem-cell transplant to kill light-chain-producing cells |
Prognosis (modern data) | Median survival 133 months in one large recent cohort | Generally shorter; more aggressive course |
The distinction matters: the same biopsy-and-stain test identifies which type you have, and the wrong treatment for either type is a dangerous mistake.
What increases the risk of developing AA amyloidosis?
The risk of AA amyloidosis rises with the underlying inflammatory disease, long-standing uncontrolled inflammation, geography and genetic variants of the SAA gene. First, the underlying disease itself: AA amyloidosis occurs in about 1 to 5% of patients with rheumatoid arthritis, juvenile idiopathic arthritis, and Crohn's disease, and more frequently in lifelong autoinflammatory conditions such as familial Mediterranean fever [4]. Second, time: the median duration of inflammation before an AA amyloidosis diagnosis is about 20 years, meaning long-unchallenged inflammation is the main risk amplifier [4]. Third, geography and era: the disease is more common in Finland, Japan, Turkey, and the Middle East, and in regions where chronic infections (tuberculosis, leprosy, chronic osteomyelitis) remain poorly controlled [3] [2].
Genetics also play a role, specific variants (alleles) of the SAA gene affect how readily the protein turns into amyloid. Ethnic differences are documented: certain SAA1 alleles raise risk in Caucasian rheumatoid arthritis patients, while other variants are linked to faster progression in Japanese patients [2].
When should you see a doctor about possible AA amyloidosis?
If you live with a chronic inflammatory condition, rheumatoid arthritis, juvenile idiopathic arthritis, Crohn's disease or ulcerative colitis, FMF or another periodic fever syndrome, or a chronic infection, and you develop any of the kidney warning signs (leg or foot swelling, foamy urine, reduced urine output) or unexplained chronic diarrhea, see a doctor promptly and mention both the symptoms and your inflammatory disease history. A simple urine protein test and kidney function panel are fast first steps.
Seek urgent care if you develop sudden breathlessness, chest pain, confusion, markedly reduced urination, or severe vomiting, these can signal rapid kidney or heart decompensation.
What is the bottom line on AA amyloidosis?
AA amyloidosis is a rare but serious complication of chronic inflammation in which misfolded serum amyloid A protein deposits on organs, kidneys above all. Fewer than 5% of people with chronic inflammatory disease ever develop it, and it usually takes many years of active inflammation to get there. But unlike several other amyloidosis types, its root cause is treatable: controlling the underlying inflammation lowers SAA, halts new deposits, and can let damaged organs recover. That is why early recognition of the kidney warning signs, foamy urine, swelling, reduced urination, in anyone with long-standing inflammation is so important.
Talk to your doctor if you have a chronic inflammatory condition and any new kidney symptoms. Ask how your condition might relate to AA amyloidosis, and whether regular urine protein and kidney function checks belong in your routine care. Early diagnosis changes the entire trajectory of this disease.
FAQ: AA Amyloidosis
What is AA amyloidosis in simple terms?
AA amyloidosis is a rare disease where chronic inflammation causes the protein serum amyloid A to misfold and build up as sticky deposits on organs, most often the kidneys. It is a complication of long-standing inflammatory diseases like rheumatoid arthritis, Crohn's disease, chronic infections, and inherited fever syndromes.
Is AA amyloidosis curable?
AA amyloidosis is treatable, and in many cases effectively controlled. Because the disease is driven by ongoing inflammation, treating the underlying condition stops new amyloid deposits from forming and can allow damaged organs, especially kidneys, to recover. Early diagnosis and treatment is key.
How rare is AA amyloidosis?
Very rare. It develops in fewer than 5% of patients with chronic inflammatory disorders, and roughly a quarter of cases have no clearly identifiable underlying cause. It is more common in Finland, Japan, Turkey, and the Middle East.
Which organs does AA amyloidosis damage?
The kidneys are affected in virtually all cases and drive the symptoms, proteinuria (foamy urine), swelling, and kidney failure. The liver and spleen enlarge, the gut causes chronic diarrhea, and clinically significant heart involvement is rare (about 5%).
What are the first symptoms of AA amyloidosis?
Swollen feet and legs, foamy or frothy urine, and peeing less than usual are the earliest kidney signals. Chronic diarrhea, enlarged liver or kidneys, low blood pressure, nausea, and vomiting also occur as the disease progresses.
How is AA amyloidosis diagnosed?
Through a tissue biopsy, usually a fat pad sample under the skin, sometimes a kidney biopsy. The tissue is stained with Congo red dye; amyloid deposits show apple-green birefringence under polarized light. The biopsy must also confirm the AA type to rule out AL amyloidosis, which needs different treatment.
What is the treatment for AA amyloidosis?
Treatment targets the root cause: controlling the underlying inflammatory disease with antimicrobials (for chronic infections), colchicine (for familial Mediterranean fever), or immunosuppressants/biologics (for autoimmune diseases). The goal is to lower SAA protein to below 10 mg/L. Kidney failure may require dialysis or, if inflammation is controlled, a transplant.
What is the life expectancy with AA amyloidosis?
Untreated disease can be terminal, with kidney failure causing death in 40 to 60% of cases. However, modern data are encouraging: a large recent cohort of AA amyloidosis patients had a median survival of 133 months (over 11 years) from diagnosis, showing that controlling the underlying inflammation transforms the outlook.
References
Cleveland Clinic. AA Amyloidosis. Cleveland Clinic. June 23, 2022. https://my.clevelandclinic.org/health/diseases/17854-amyloidosis-aa
Real de Asúa D, et al. Systemic AA amyloidosis: epidemiology, diagnosis, and management. Clinical Epidemiology. 2014;6:369-377. PMID 25378951. https://doi.org/10.2147/CLEP.S39981
Orphanet. AA amyloidosis. Orphanet. September 2021. https://www.orpha.net/en/disease/detail/85445
Reactive systemic amyloidosis, AA amyloidosis. In: Hochberg MC, Silman AJ, Smolen JS, Weinblatt ME, Weisman MH, eds. Rheumatology. 6th ed. Elsevier; 2014. https://shop.elsevier.com/books/rheumatology-2-volume-set/hochberg/978-0-323-09138-1
Thorne J, et al. Serum Amyloid A Protein-Associated Kidney Disease: Presentation, Diagnosis, and Management. Kidney Medicine. 2022;4(8):100504. PMID 35879979. https://doi.org/10.1016/j.xkme.2022.100504
Gurung R, et al. Renal Amyloidosis: Presentation, Diagnosis, and Management. American Journal of Medicine. 2022;135 Suppl 1:S38-S43. PMID 35085515. https://doi.org/10.1016/j.amjmed.2022.01.003
Ahbap E, et al. Outcome of 121 patients with renal amyloid A amyloidosis. Journal of Research in Medical Sciences. 2014;19(7):644-649. PMID 25364365. https://pubmed.ncbi.nlm.nih.gov/25364365/
Bustamante JG, et al. Amyloidosis. StatPearls. July 31, 2023. https://www.ncbi.nlm.nih.gov/books/NBK470285/
Brunger AF, et al. Causes of AA amyloidosis: a systematic review. Amyloid. 2020;27(1):1-12. PMID 31766892. https://doi.org/10.1080/13506129.2019.1693359
García-Pavía P, et al. Amyloidosis. Also a heart disease. Revista Española de Cardiología. 2011;64(9):797-808. PMID 21775043. https://doi.org/10.1016/j.recesp.2011.05.003
Lachmann HJ, et al. Natural history and outcome in systemic AA amyloidosis. New England Journal of Medicine. 2007;356(23):2361-2371. PMID 17554117. https://doi.org/10.1056/NEJMoa070265
Dember LM, et al. Eprodisate for the treatment of renal disease in AA amyloidosis. New England Journal of Medicine. 2007;356(23):2349-2360. PMID 17554116. https://doi.org/10.1056/NEJMoa065644



Comments